Schedule Your Free Consultation

A dental implant gives you a root. But the restoration is what gives you a smile.

The implant — a titanium cylinder placed into the jawbone — is the foundation. It’s hidden beneath the gums, invisible to the world. What people see, what you eat with, what you smile with every day, is the restoration: the crown, bridge, or prosthesis that connects to that implant and becomes your new tooth.

At Michael Kriston DDS in Danville, implant restorations are approached with the same cosmetic precision that drives everything we do. Dr. Kriston doesn’t just attach a tooth to an implant — he designs a restoration that matches the shade, shape, translucency, and gum line contour of your natural teeth so seamlessly that no one can tell the difference. With 38 years of experience restoring implants and advanced training in cosmetic dentistry, he brings an artist’s eye to a procedure that many practices treat as purely mechanical.

Because the cosmetic result of an implant depends as much on the restoration as on the surgical placement, having a restorative dentist who understands aesthetics at this level is what separates a good implant outcome from an exceptional one.

Contact

Understanding the Implant-to-Restoration Connection

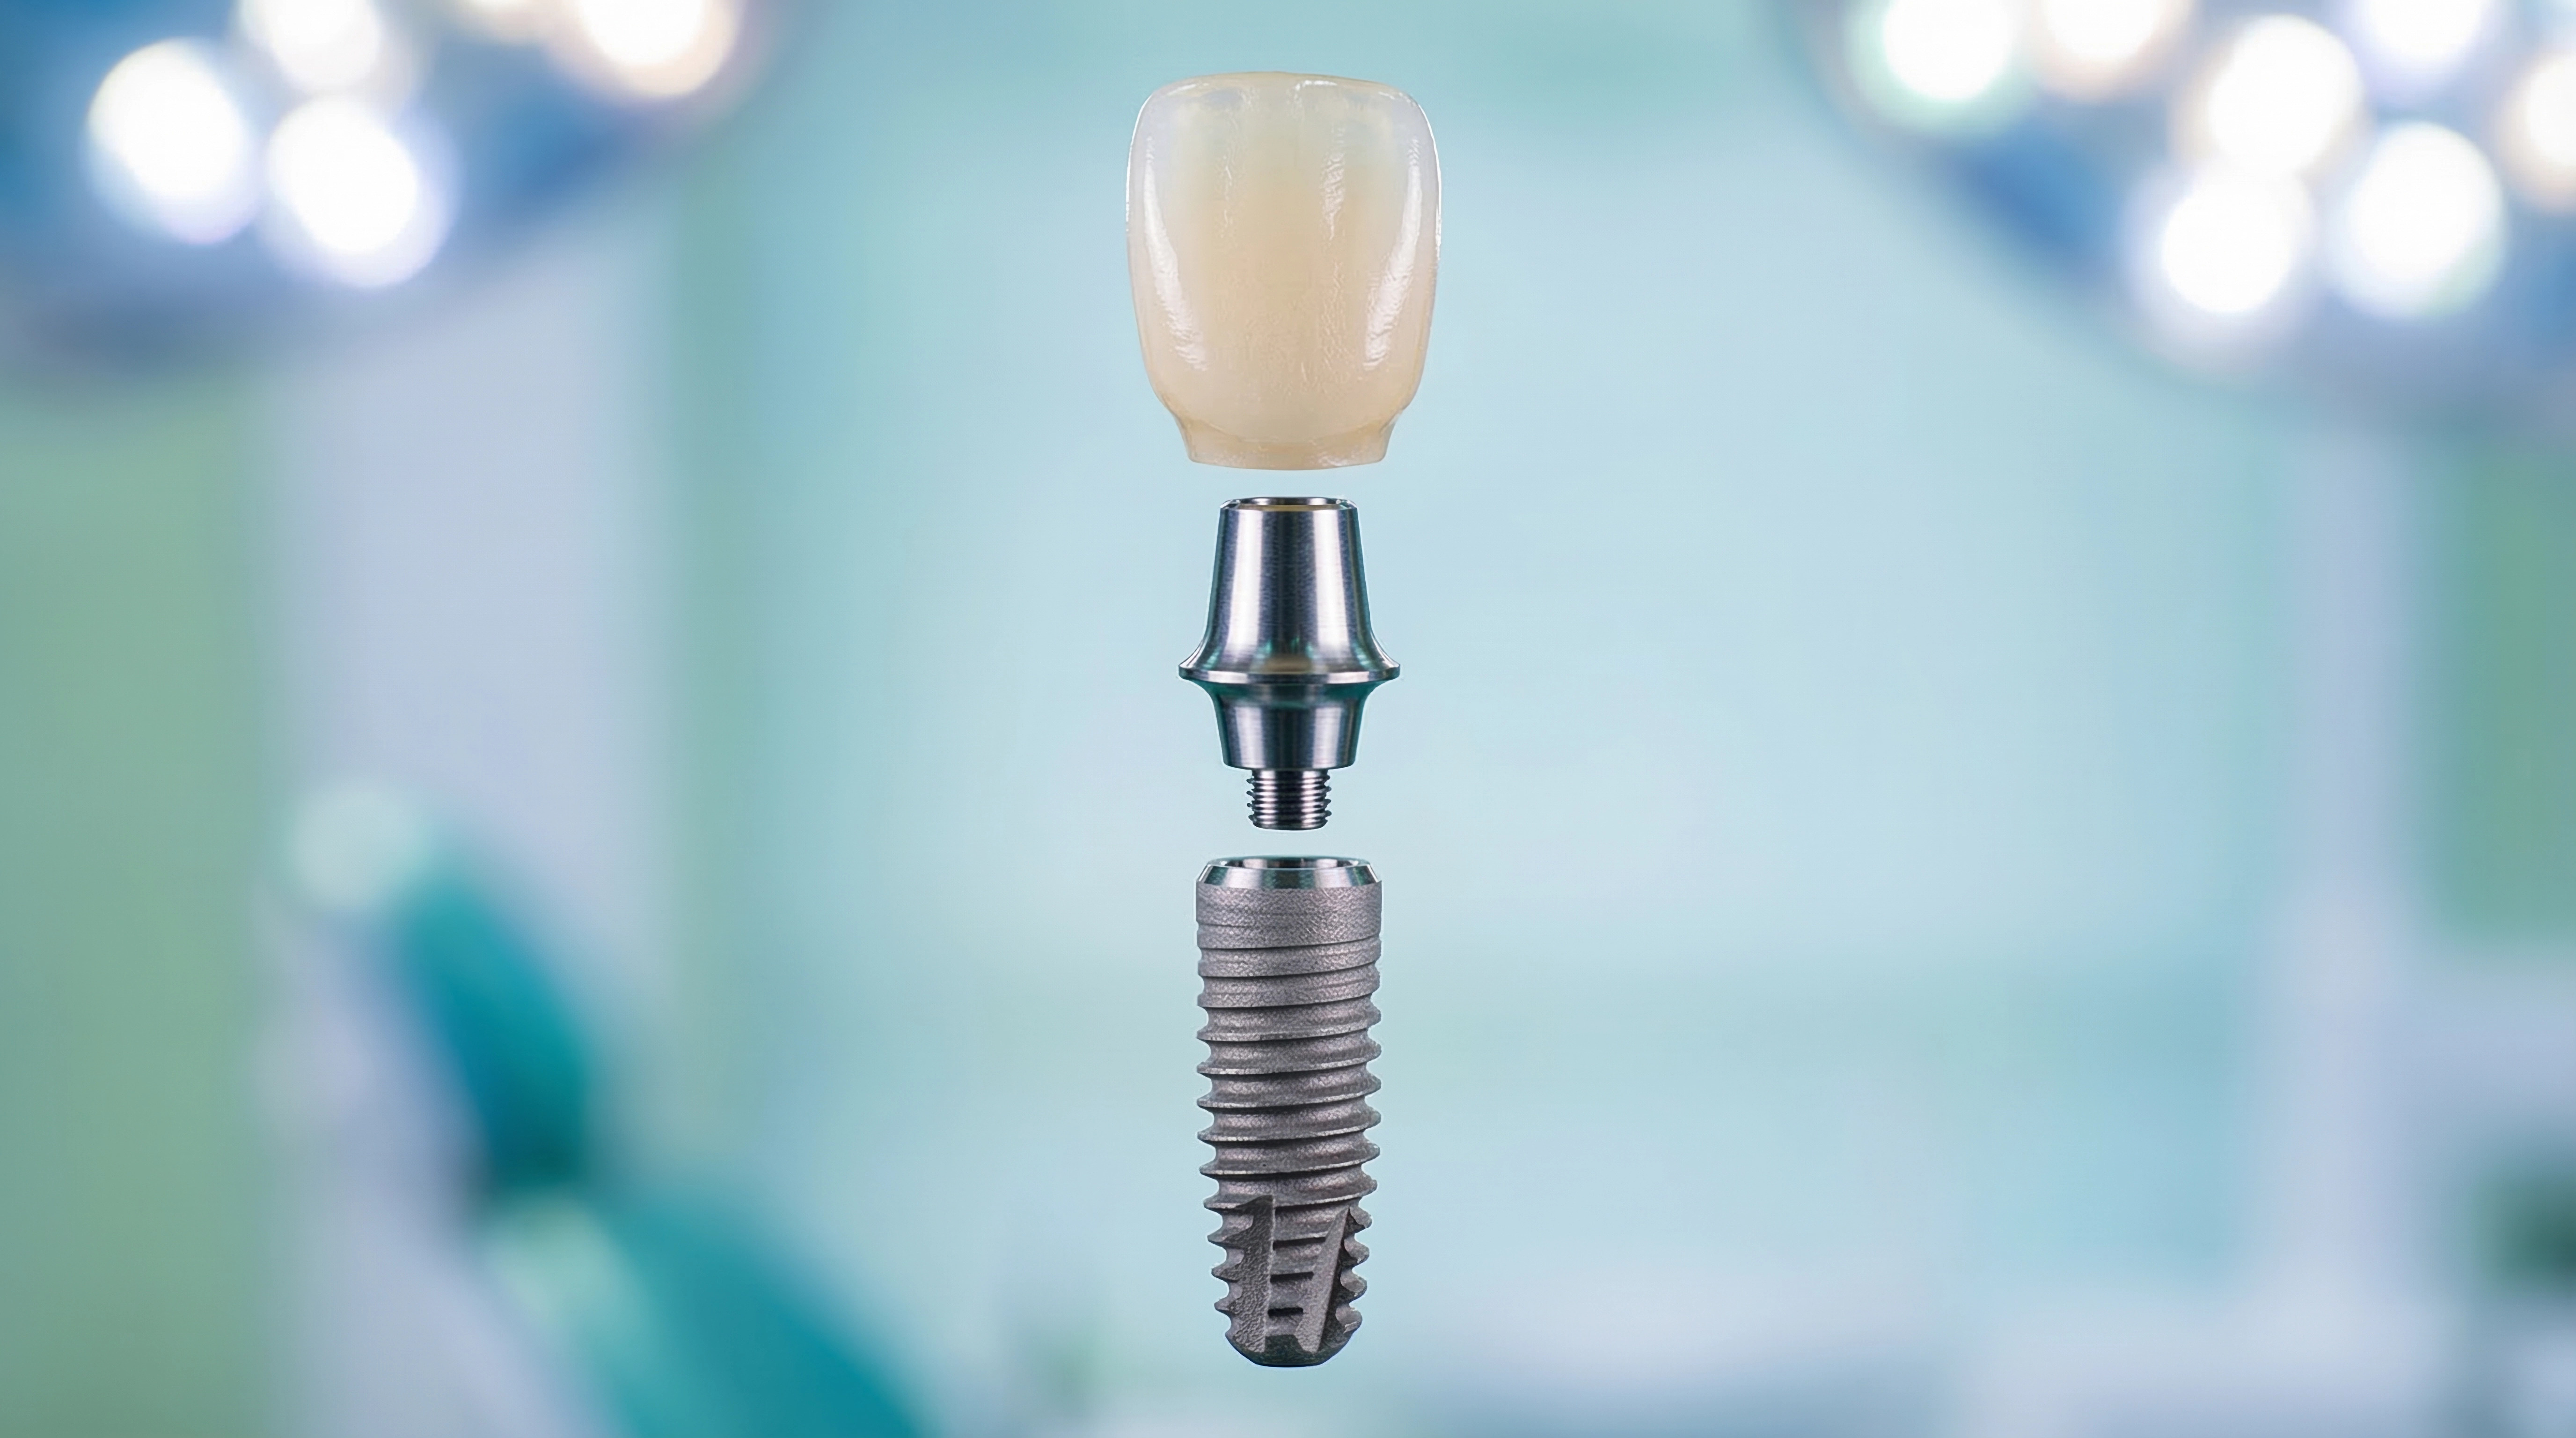
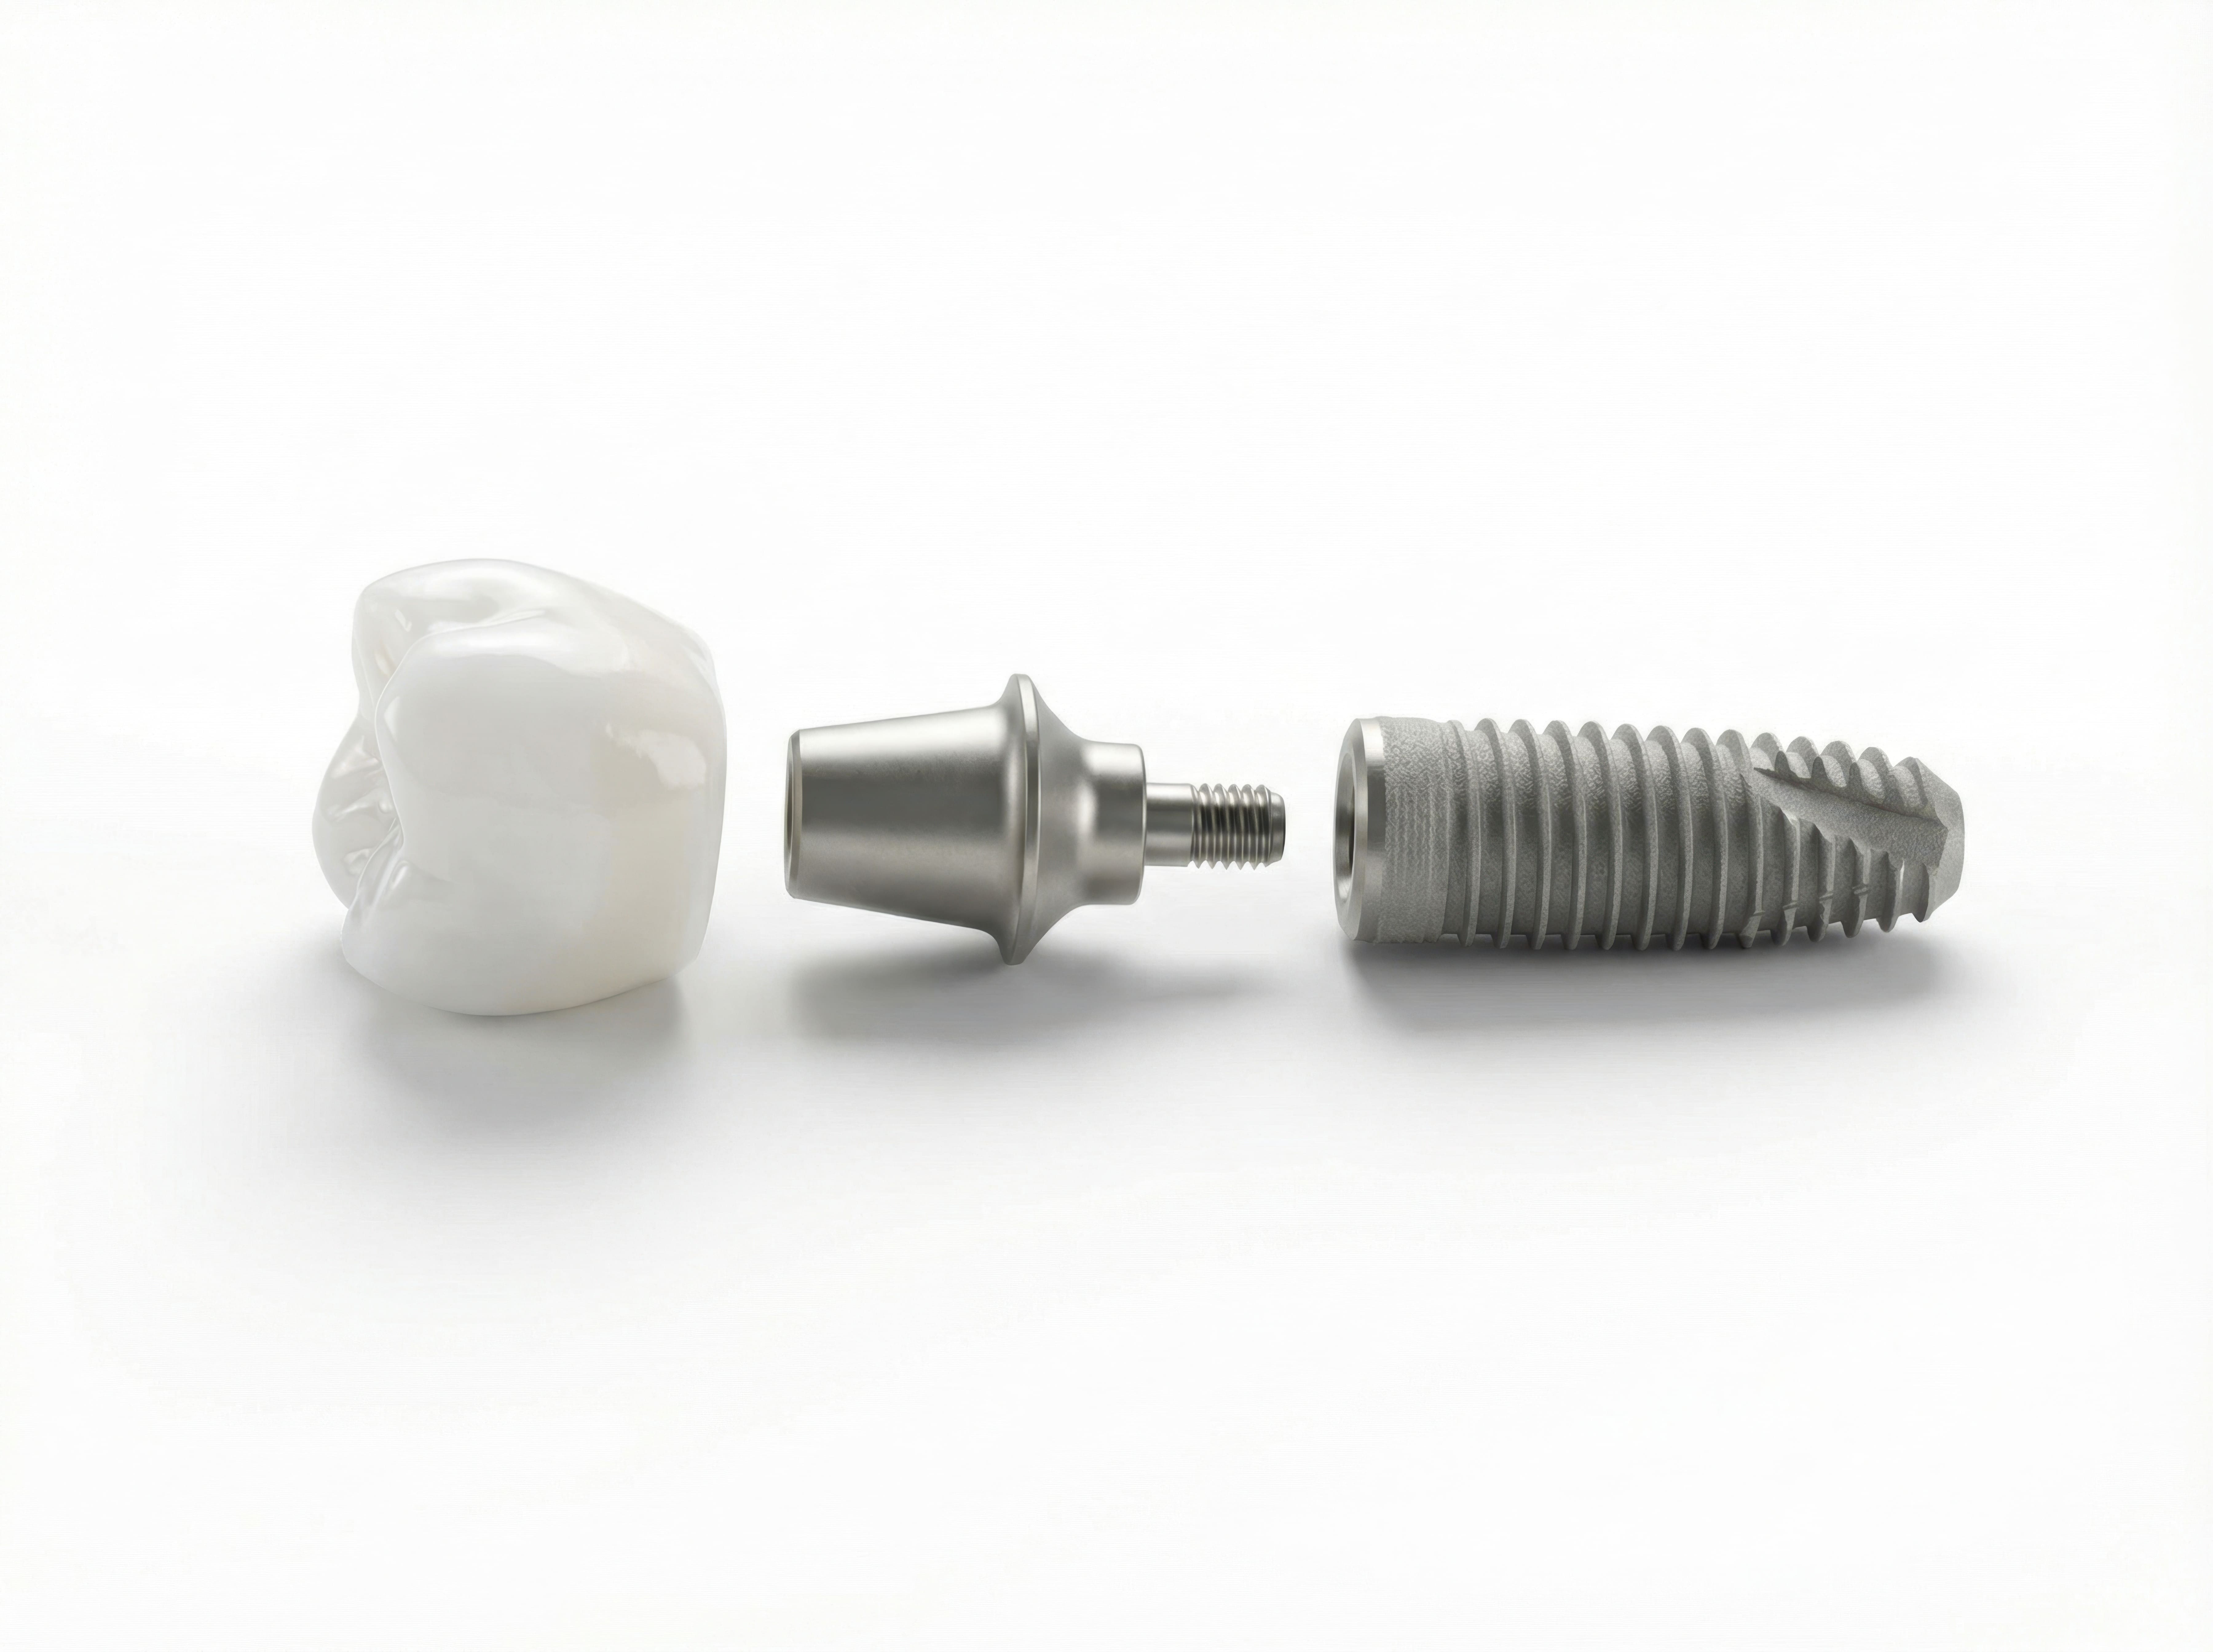
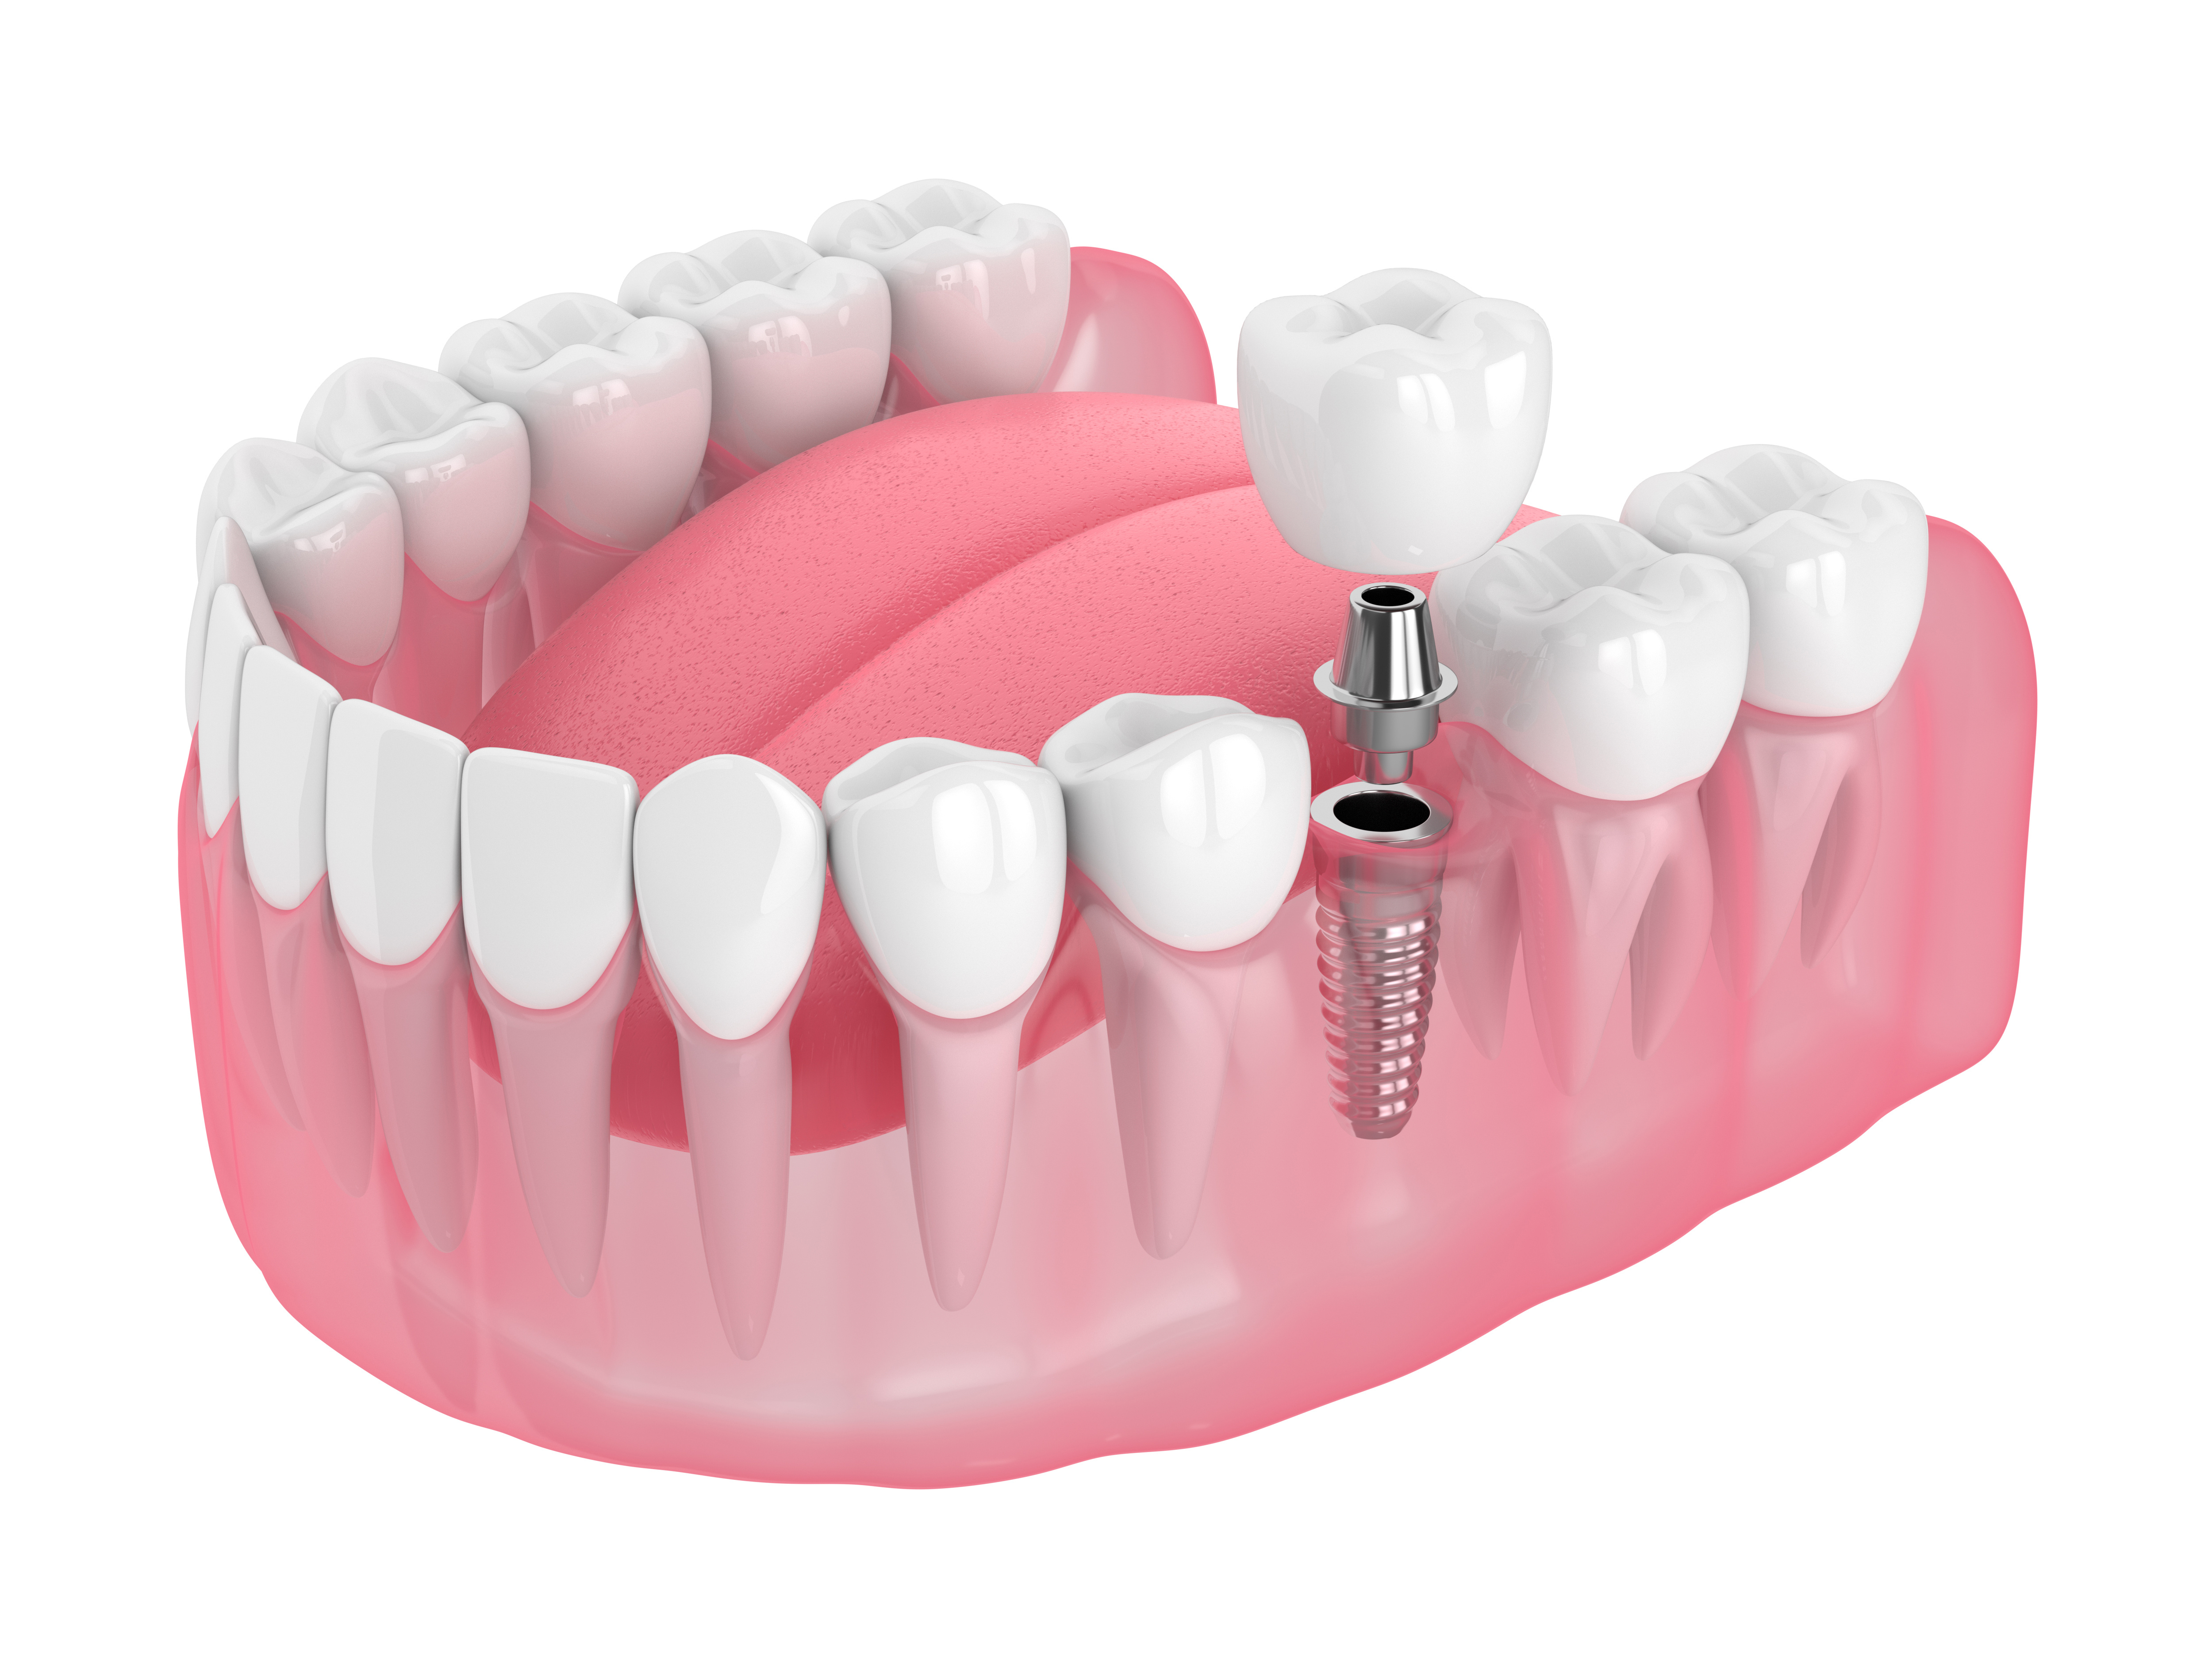
To appreciate why the cosmetic details matter so much, it helps to understand how an implant restoration is constructed. There are three components:

The implant. A titanium cylinder surgically placed into the jawbone. Titanium has been used for decades in joint replacements and is extremely compatible with the body. Over two to three months, the bone fuses with the titanium through a process called osseointegration, creating an incredibly solid anchor — stronger, in many ways, than a natural tooth root.

The abutment. A connector piece that screws into the top of the implant and extends above the gum line. The abutment is what the final restoration (crown, bridge, or denture) attaches to. The material, shape, and color of the abutment directly affect the cosmetic result — and this is where most patients (and many dentists) don’t realize how much the details matter.

The restoration. The visible crown, bridge, or prosthesis that replaces your missing tooth or teeth. This is what you see, what you chew with, and what needs to look completely natural.

The Abutment Decision — Why It Matters for Your Smile

This is one of the most overlooked aspects of implant dentistry, and it’s where Dr. Kriston’s cosmetic expertise makes a real difference.

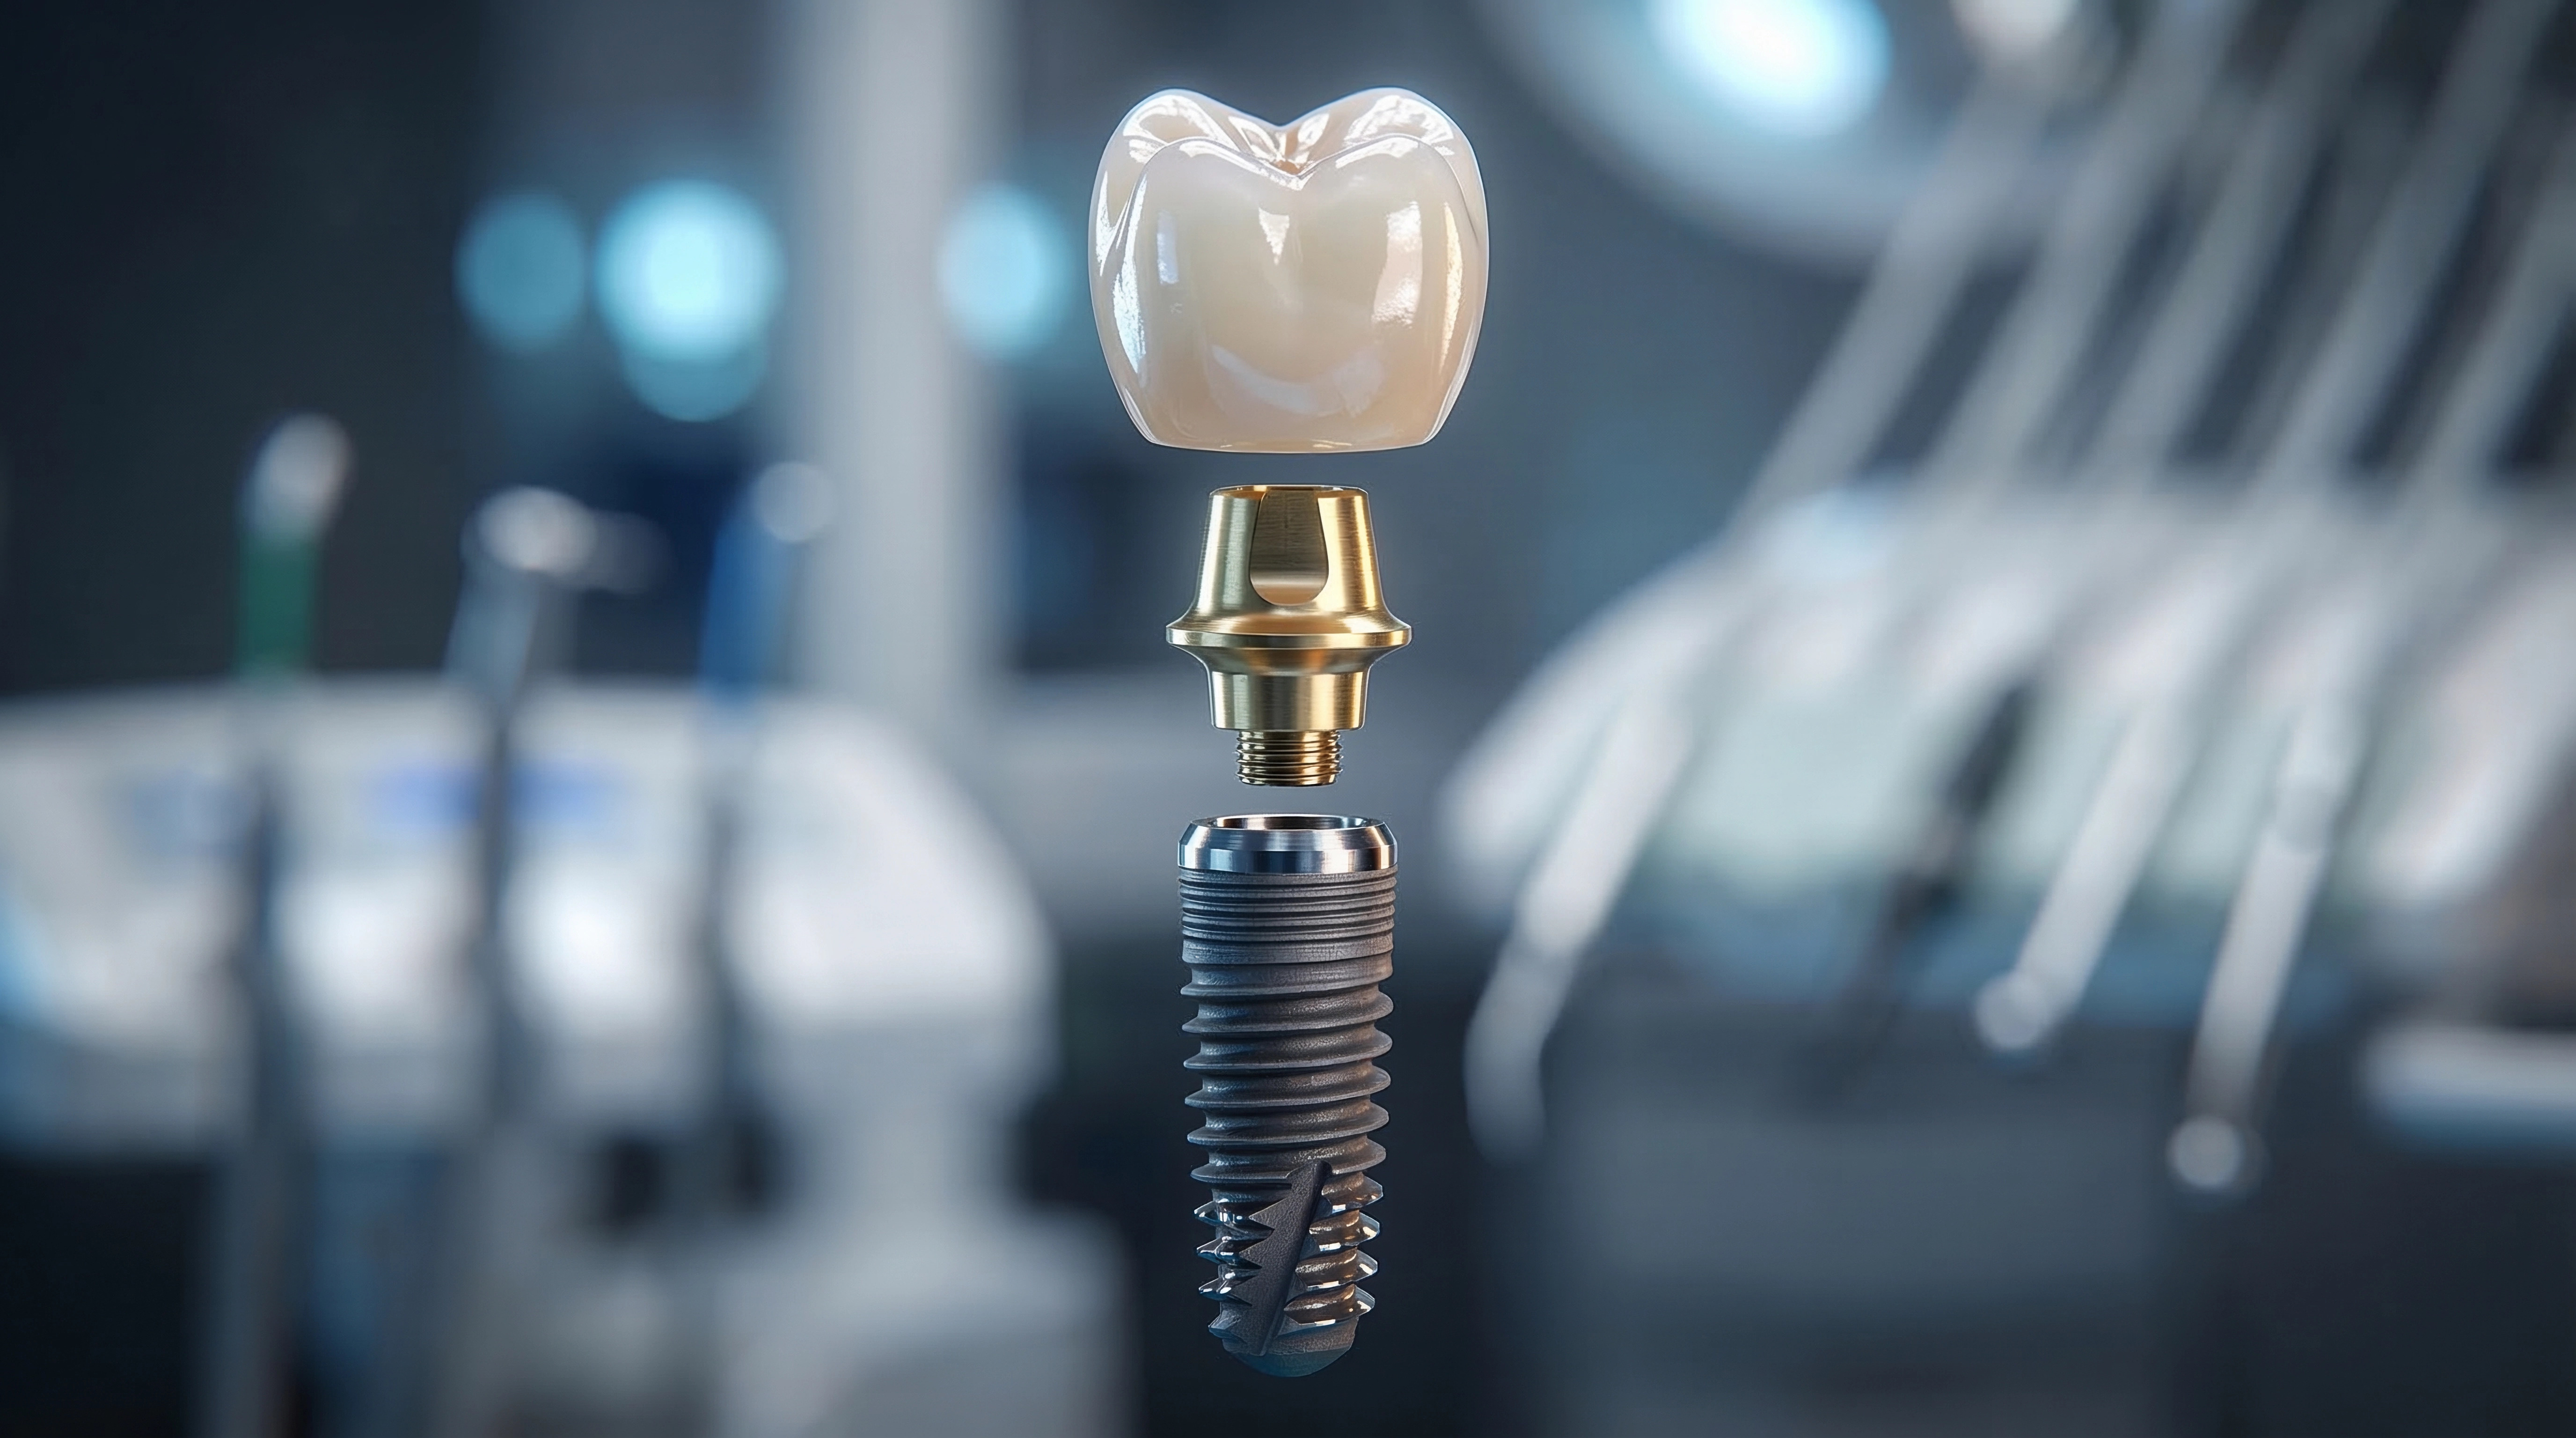
The standard abutment material is titanium — the same metal as the implant. Titanium is extremely strong and has a long, proven track record. But it’s gray. And that gray color can show through thin gum tissue, especially in the esthetic zone (the front teeth and any area visible when you smile or talk), creating a shadowed, unnatural appearance at the gum line.

There are several solutions, and Dr. Kriston selects the right one based on your specific situation:

Gold-Tone Anodized Titanium — Dr. Kriston’s Preferred Solution

The most effective way to address the gray titanium issue in the esthetic zone is to anodize the surface of the titanium abutment with a gold tone. This process changes the surface color from gray to a warm gold that closely mimics the natural shade of the core of a tooth beneath the enamel.

Why is this Dr. Kriston’s preferred approach? Because it gives you the best of both worlds: the full strength and proven reliability of titanium, with a warm undertone that prevents the gray shadow that can show through the gums. The gold-tone abutment essentially disappears — the gum tissue reflects a natural, healthy color rather than a grayish hue.

This is a detail that many practices skip entirely. But in the esthetic zone — where your smile is on display — it’s the kind of detail that makes the difference between a restoration that looks real and one that looks like an implant.

Zirconia Abutments — White, but with Trade-Offs

Zirconia is a white ceramic material that can also be used for abutments. Its white appearance is cosmetically appealing, and it eliminates any concern about gray showing through the tissue.

However, zirconia abutments are not as strong as titanium. In the esthetic zone, where bite forces are generally lower (front teeth), zirconia can work well. But for areas with heavier chewing forces, or for patients who clench or grind, the reduced strength of zirconia can be a concern. Dr. Kriston evaluates each case individually and recommends zirconia only when the clinical situation supports it.

Solving an Existing Gray Abutment

What if you already have a dental implant with a gray titanium abutment and the crown has come off or been damaged? Do you need to replace the entire abutment?

Not necessarily. Dr. Kriston can use an opaque zirconia layer inside the new crown to mask the gray color of the existing titanium abutment. This technique blocks the gray from showing through without requiring the abutment to be removed and replaced with a gold-tone version. It’s a practical, conservative solution that saves you the additional surgery of changing the abutment while still delivering a cosmetically excellent result.

This kind of problem-solving is what happens when your restorative dentist understands both the cosmetic requirements and the clinical realities of implant dentistry.

The Esthetic Zone — Where Cosmetics Meet Complexity

The esthetic zone applies primarily to the upper front teeth — and it’s where the cosmetic stakes of an implant restoration are highest. This is the area that’s on display every time you smile, laugh, or speak. Getting the restoration right in the esthetic zone requires an analysis that goes far beyond simply placing a crown on an implant.

What Dr. Kriston Analyzes in
the Esthetic Zone

Before any implant work begins in the esthetic zone, Dr. Kriston performs a detailed smile analysis
evaluating four key elements:

Lip line. How high do your lips lift when you smile? How much of your teeth and gums are revealed during natural speech? An ideal, beautiful smile shows as much of the teeth as possible — ideally all of the teeth up to the gum line, with no more than 1 to 2 millimeters of gum tissue visible above the teeth. A “high lip line” — where significantly more gum is visible when smiling or talking — demands much more attention to the restoration because every millimeter of the gum line, the restoration margin, and the tissue contour is on display.

Contour of the gum line. The gum tissue around the restoration must follow the same natural curves as the gums around your adjacent teeth. The gingival zenith (the highest point of the gum curve on each tooth) needs to be positioned correctly and symmetrically. If the gum contour around an implant restoration doesn’t match the natural teeth beside it, the asymmetry is immediately noticeable.

Tooth proportions. The width-to-length ratio of the restoration must match the proportions of the surrounding natural teeth. A restoration that’s too narrow, too wide, too long, or too short will look out of place regardless of how perfectly the shade matches. These proportions are also affected by how much bone and soft tissue is available — which directly connects to the FP-1, FP-2, and FP-3 classifications described below.

Symmetry within the smile. Mirror-image teeth (the central incisors, the lateral incisors, the canines) should be the same length, width, and gum line height on both sides of the midline. When an implant replaces one of these teeth, the restoration must precisely match its twin on the opposite side of the smile — in shade, shape, gum contour, and proportions.


Understanding Your Unique Smile Potential

It’s important to understand that not every patient has the bone structure or muscle attachments of the lips to support the ideal esthetic outcome. Some patients have naturally high lip lines that expose significant gum tissue. Others have lost bone in the esthetic zone from trauma, delayed treatment, or prior extractions without bone grafting. These structural realities place limits on what any restoration — however skillfully designed — can achieve.

This is precisely why Dr. Kriston believes the final restoration — whether fixed or removable — must be discussed and designed before implant surgery, not after. The patient needs to understand from the outset what is realistically achievable given their bone levels, gum tissue, lip dynamics, and facial structure. Surprises after surgery are not acceptable when the outcome affects your smile.

In Dr. Kriston’s practice, this pre-surgical consultation is a core part of every implant case in the esthetic zone. He shows patients what type of restoration their anatomy supports (FP-1, FP-2, or FP-3), explains why, and discusses what — if anything — can be done to improve the esthetic possibilities (such as bone grafting to preserve or rebuild the ridge). The goal is to maximize facial aesthetics as much as possible for the patient’s confidence, while being honest about limitations.

This conversation should happen with the restorative dentist before the surgeon places the implant. The surgeon places the foundation; the restorative dentist designs what the world sees. If the restorative dentist isn’t involved until after surgery, opportunities to optimize the esthetic outcome may have already been missed.

The Esthetic Zone Classification System

In implant dentistry, restorations in the esthetic zone are classified by how much hard tissue (tooth and bone) and soft tissue (gums) needs to be replaced. This classification system helps Dr. Kriston plan the exact type of restoration that will deliver the most natural result for your specific situation — and it’s what he discusses with patients during the pre-surgical consultation so expectations are set clearly from the start.

Fixed Implant Restorations

These restorations are permanently attached to the implant(s). They are not removable by the patient and function just like natural teeth. They can replace a single tooth or multiple teeth.

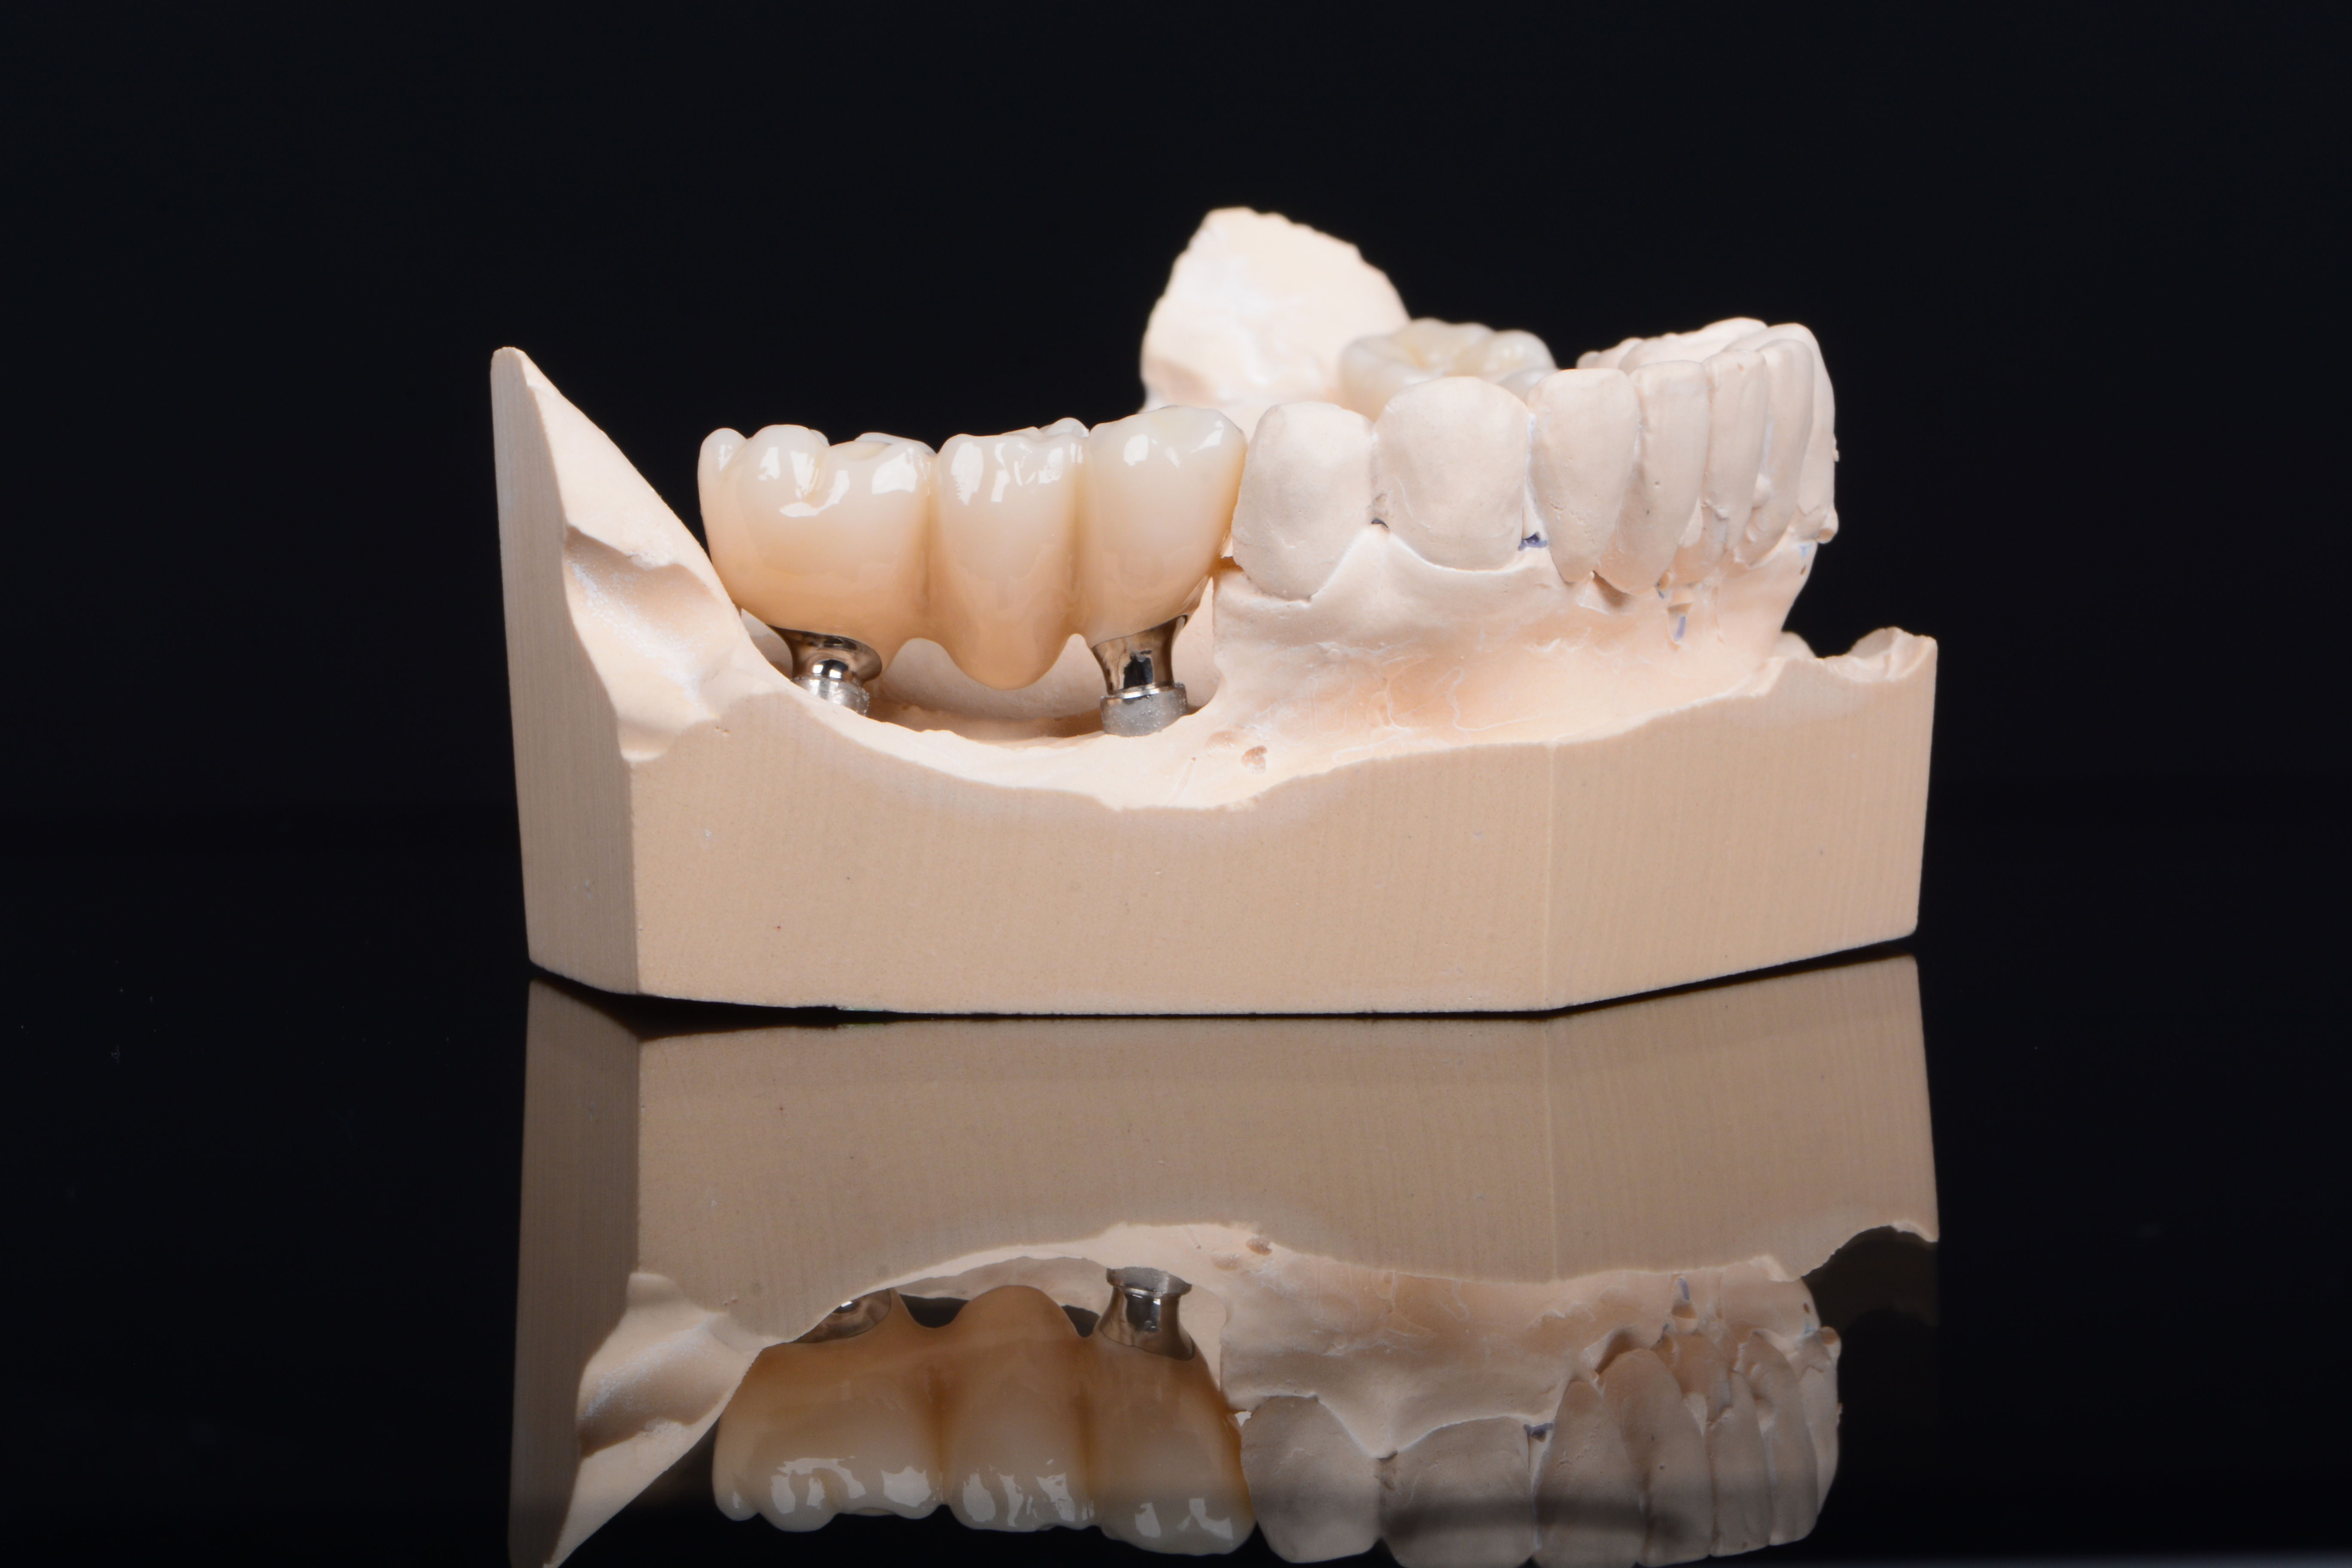
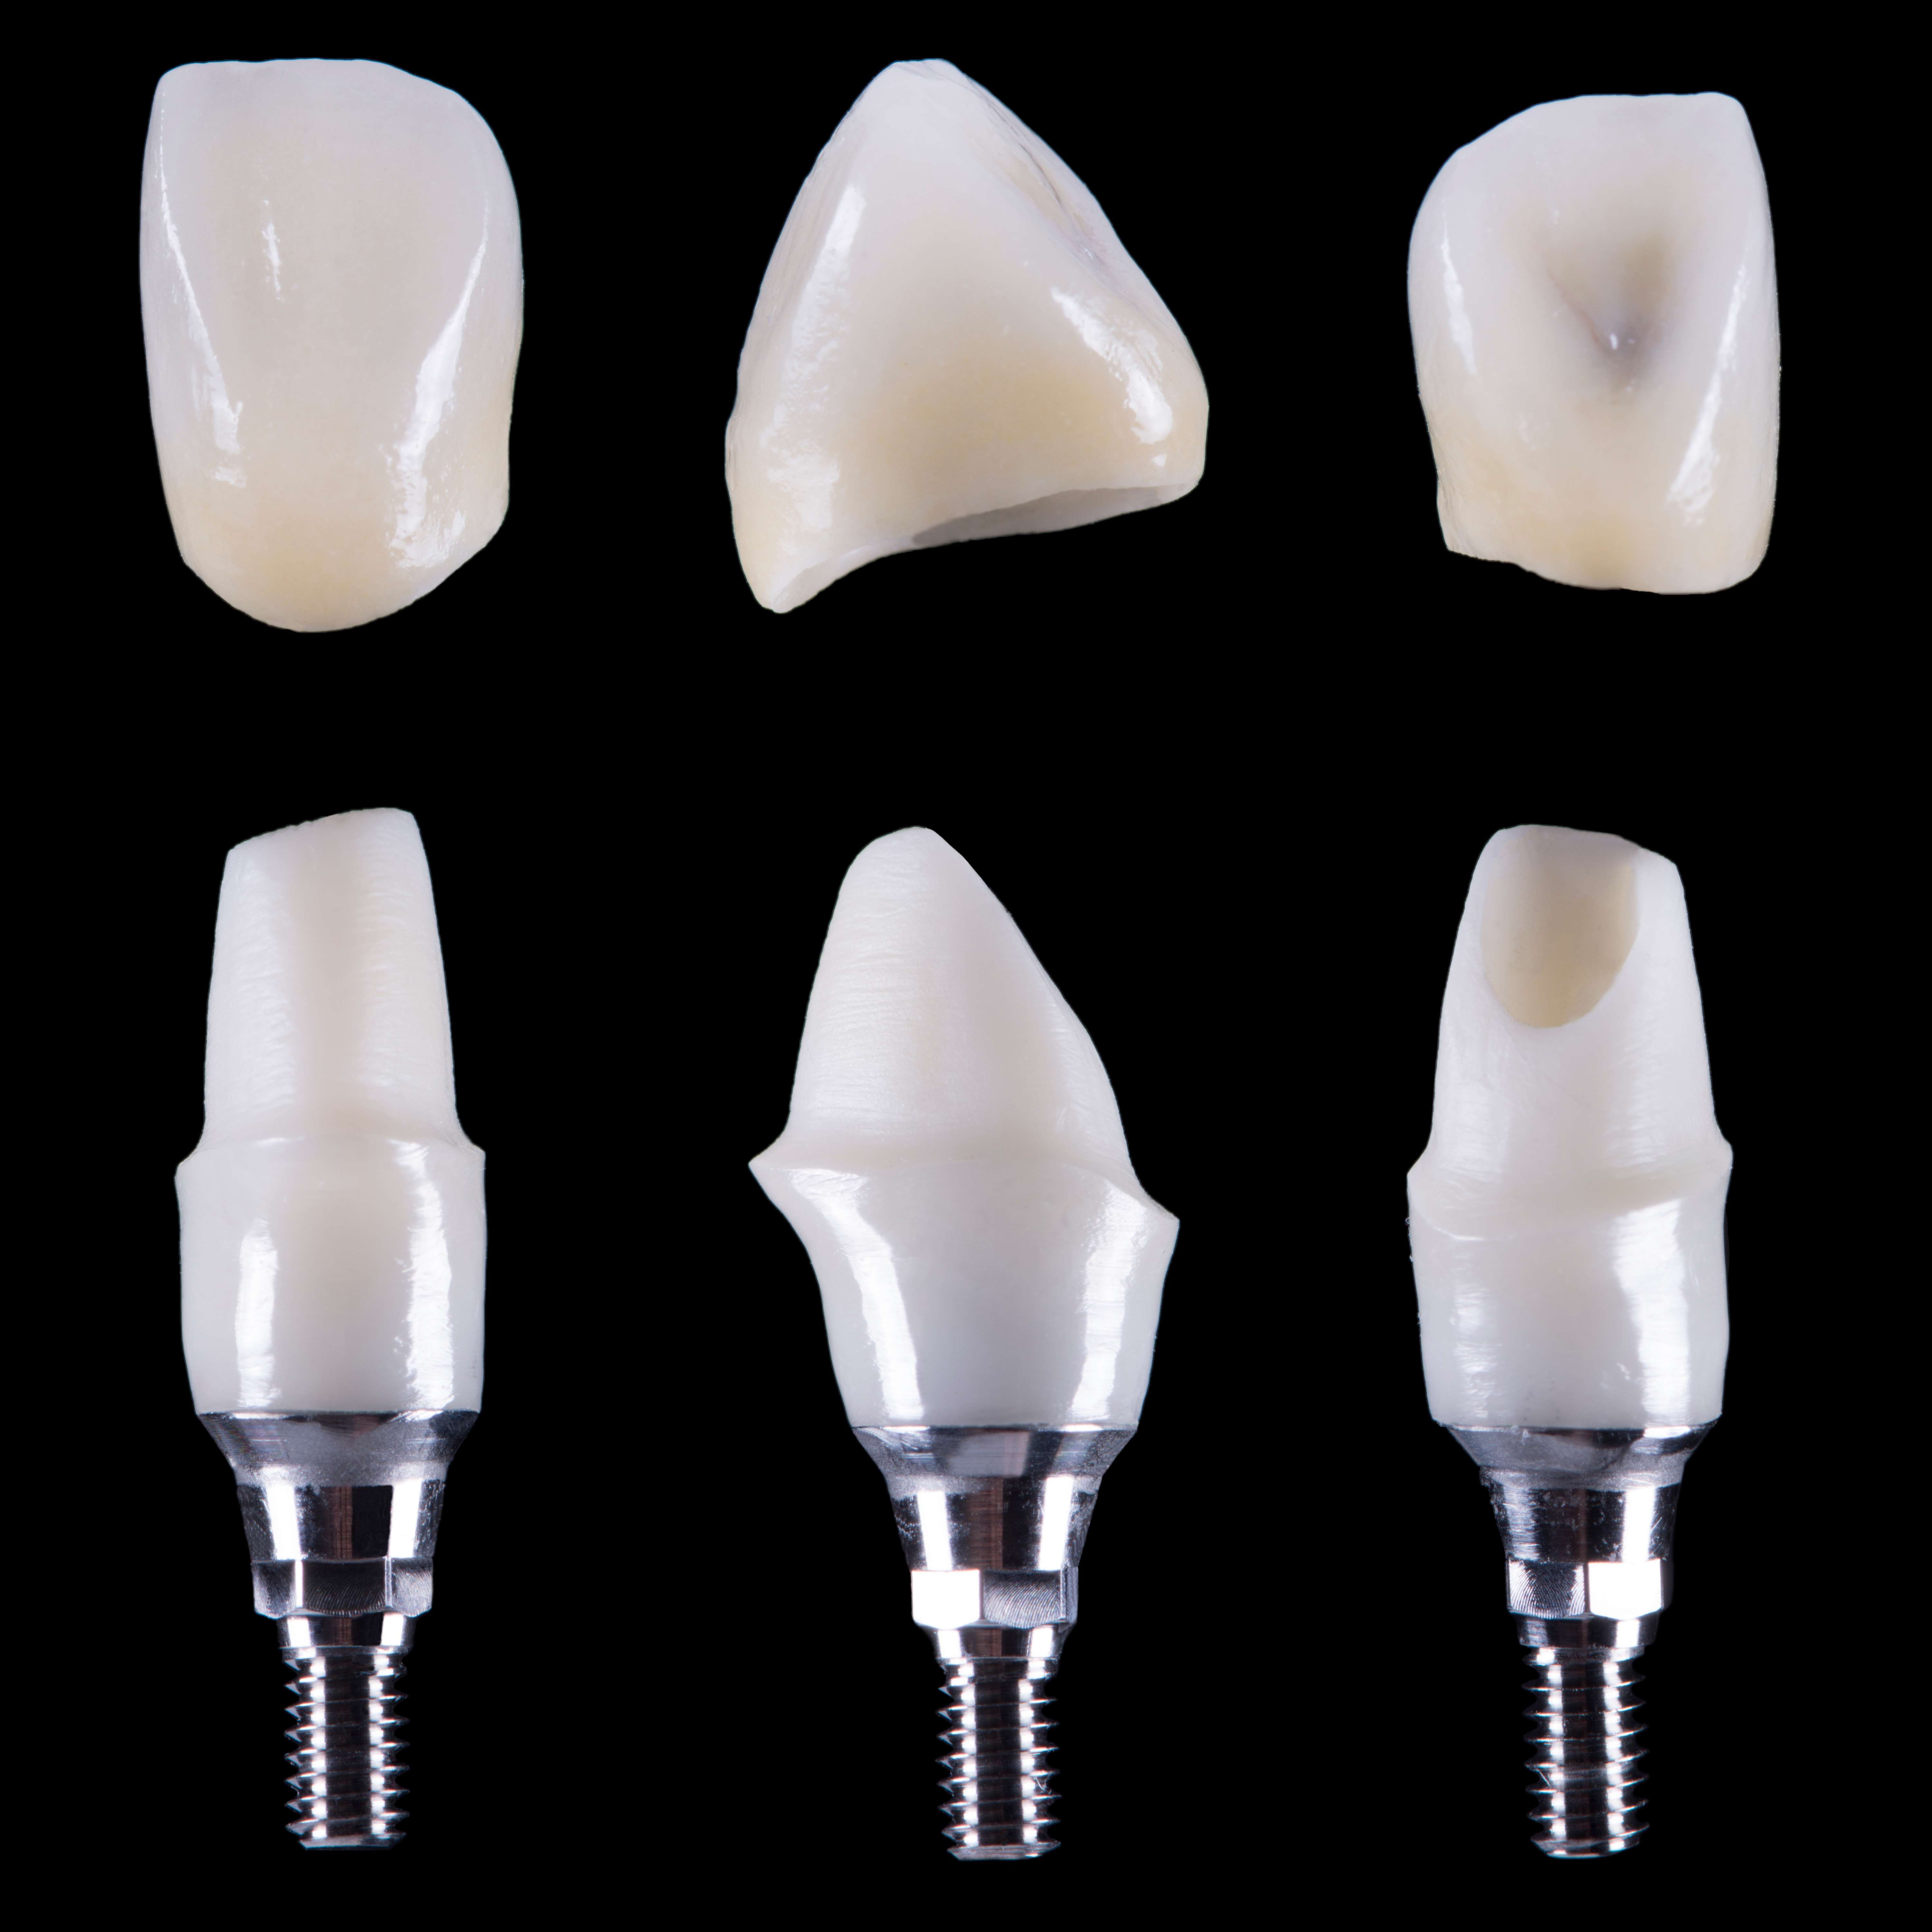
FP-1: Fixed Prosthesis, Type 1 — Crown Replacement Only

An FP-1 replaces just the crown portion of the tooth — the enamel and visible structure above the gum line. This is the ideal scenario: enough bone and gum tissue have been preserved (or were never lost) that the restoration only needs to replicate the natural tooth itself. The result looks exactly like a natural tooth emerging from healthy gums.

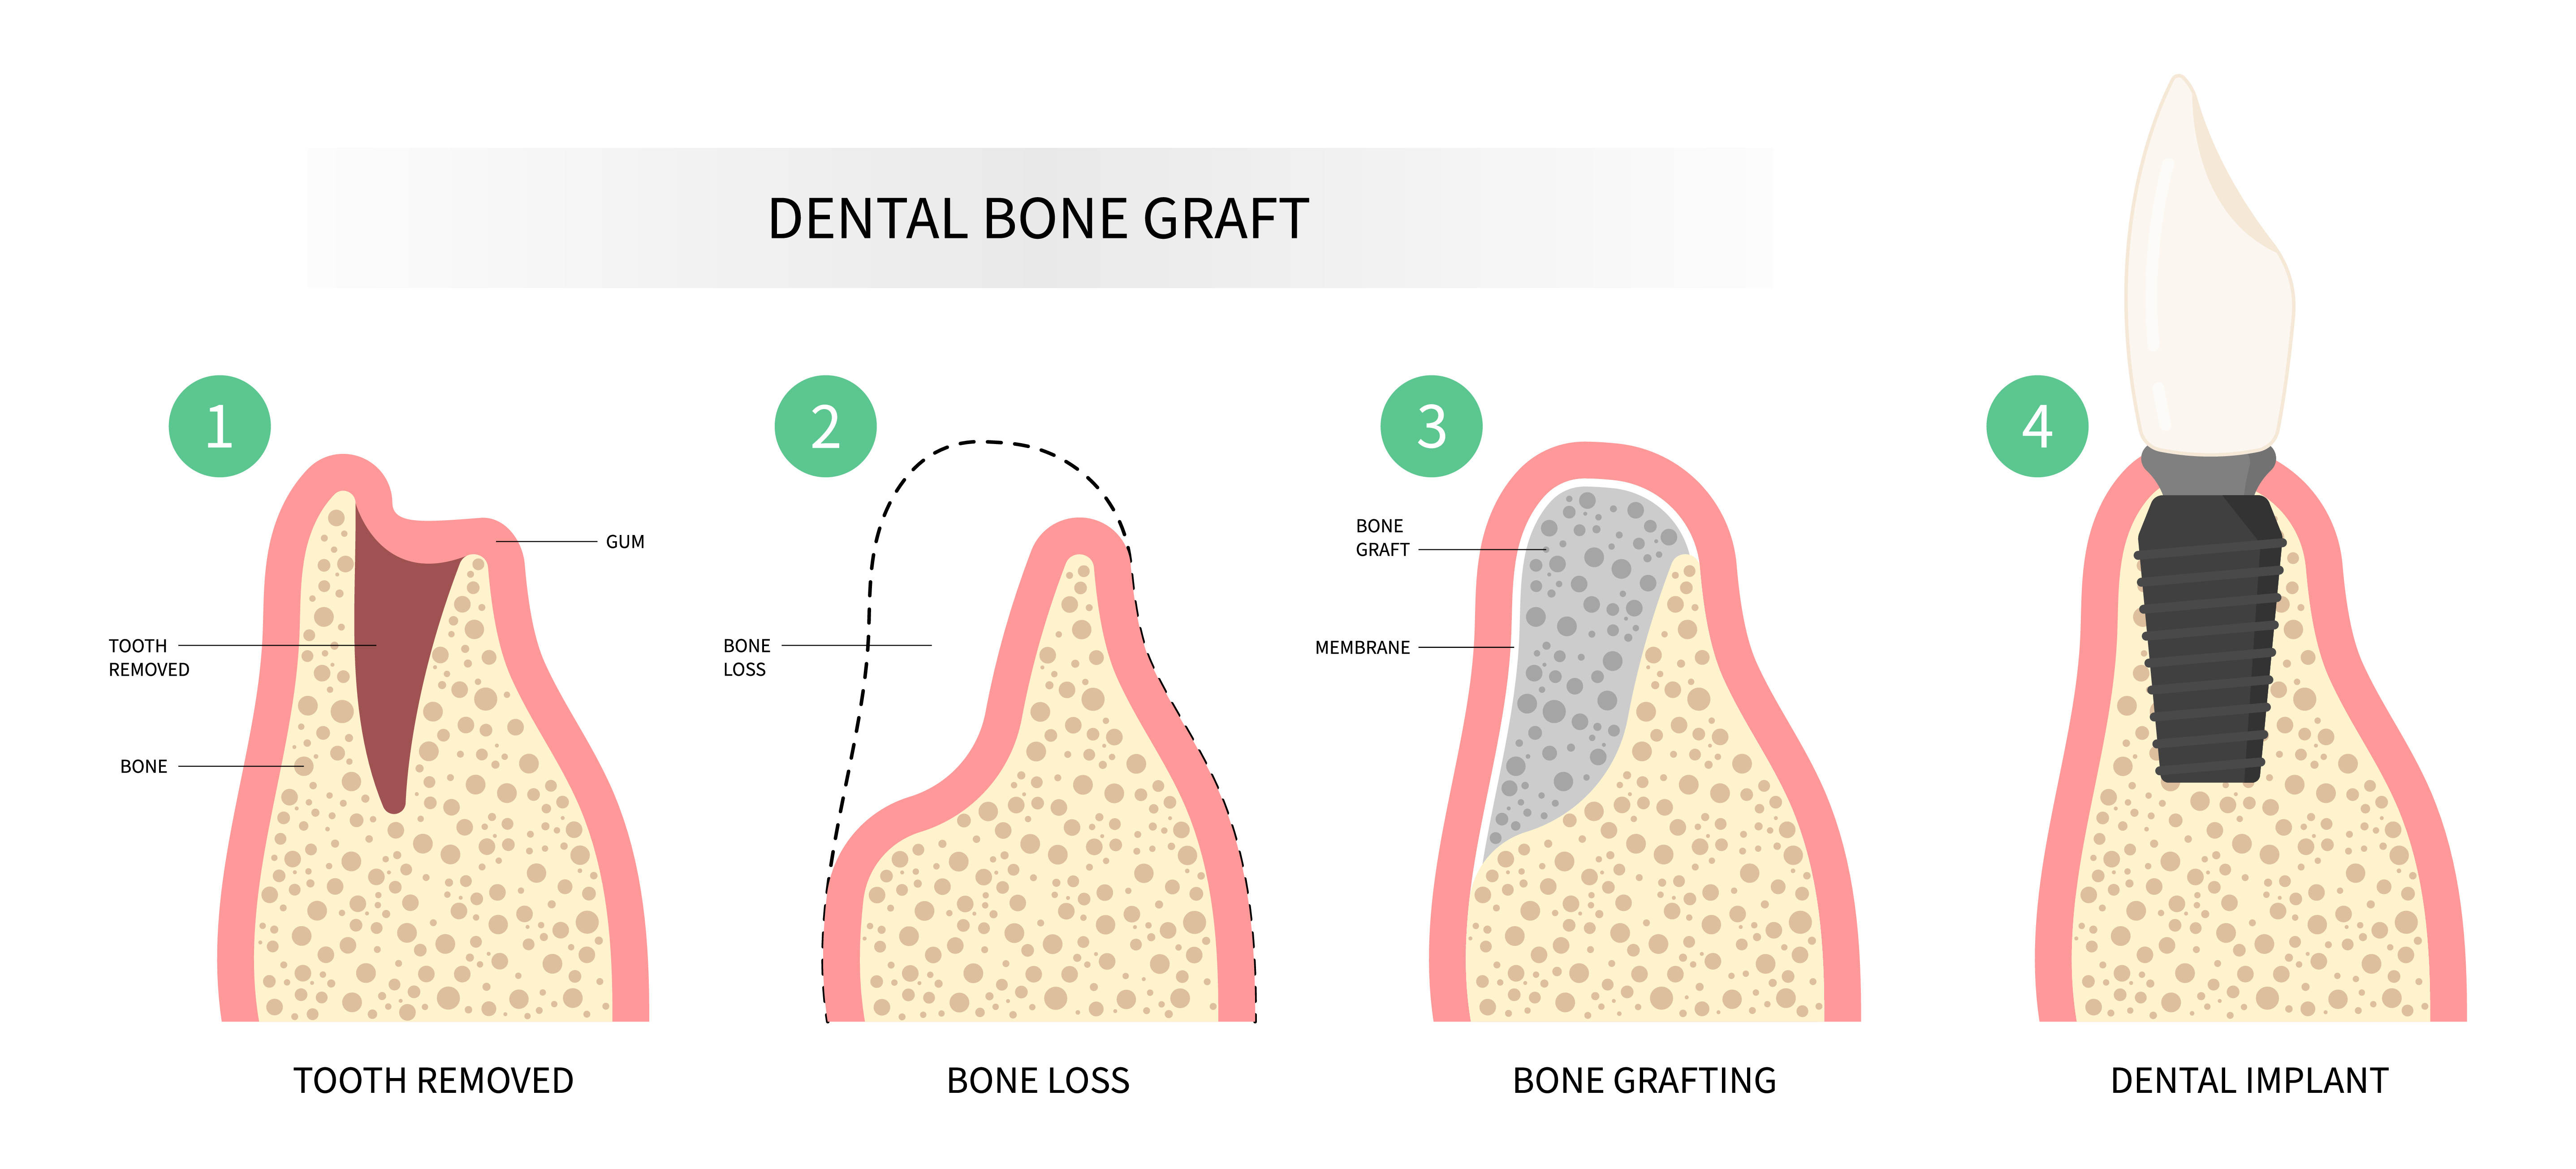
FP-1 restorations are possible when bone grafting was performed at the time of extraction (or the implant was placed immediately after extraction), preserving the bone height and soft tissue contour. This is one of the strongest arguments for proactive bone grafting — it keeps the FP-1 option available.

FP-2: Fixed Prosthesis, Type 2 — Crown and Partial Root Replacement

When some bone has been lost but the deficiency is moderate, the restoration needs to be slightly longer than a natural tooth to fill the space. An FP-2 replaces the crown and part of the root area with an elongated all-white restoration. The tooth appears a bit longer than its neighbors, but the material is entirely tooth-colored — there’s no visible pink or metal.

FP-2 restorations are common when there’s been some time between tooth loss and implant placement, allowing partial bone resorption. The result is still very cosmetically acceptable, especially in areas where the full tooth length isn’t visible.

FP-3: Fixed Prosthesis, Type 3 — Crown, Root, and Ridge Defect Replacement

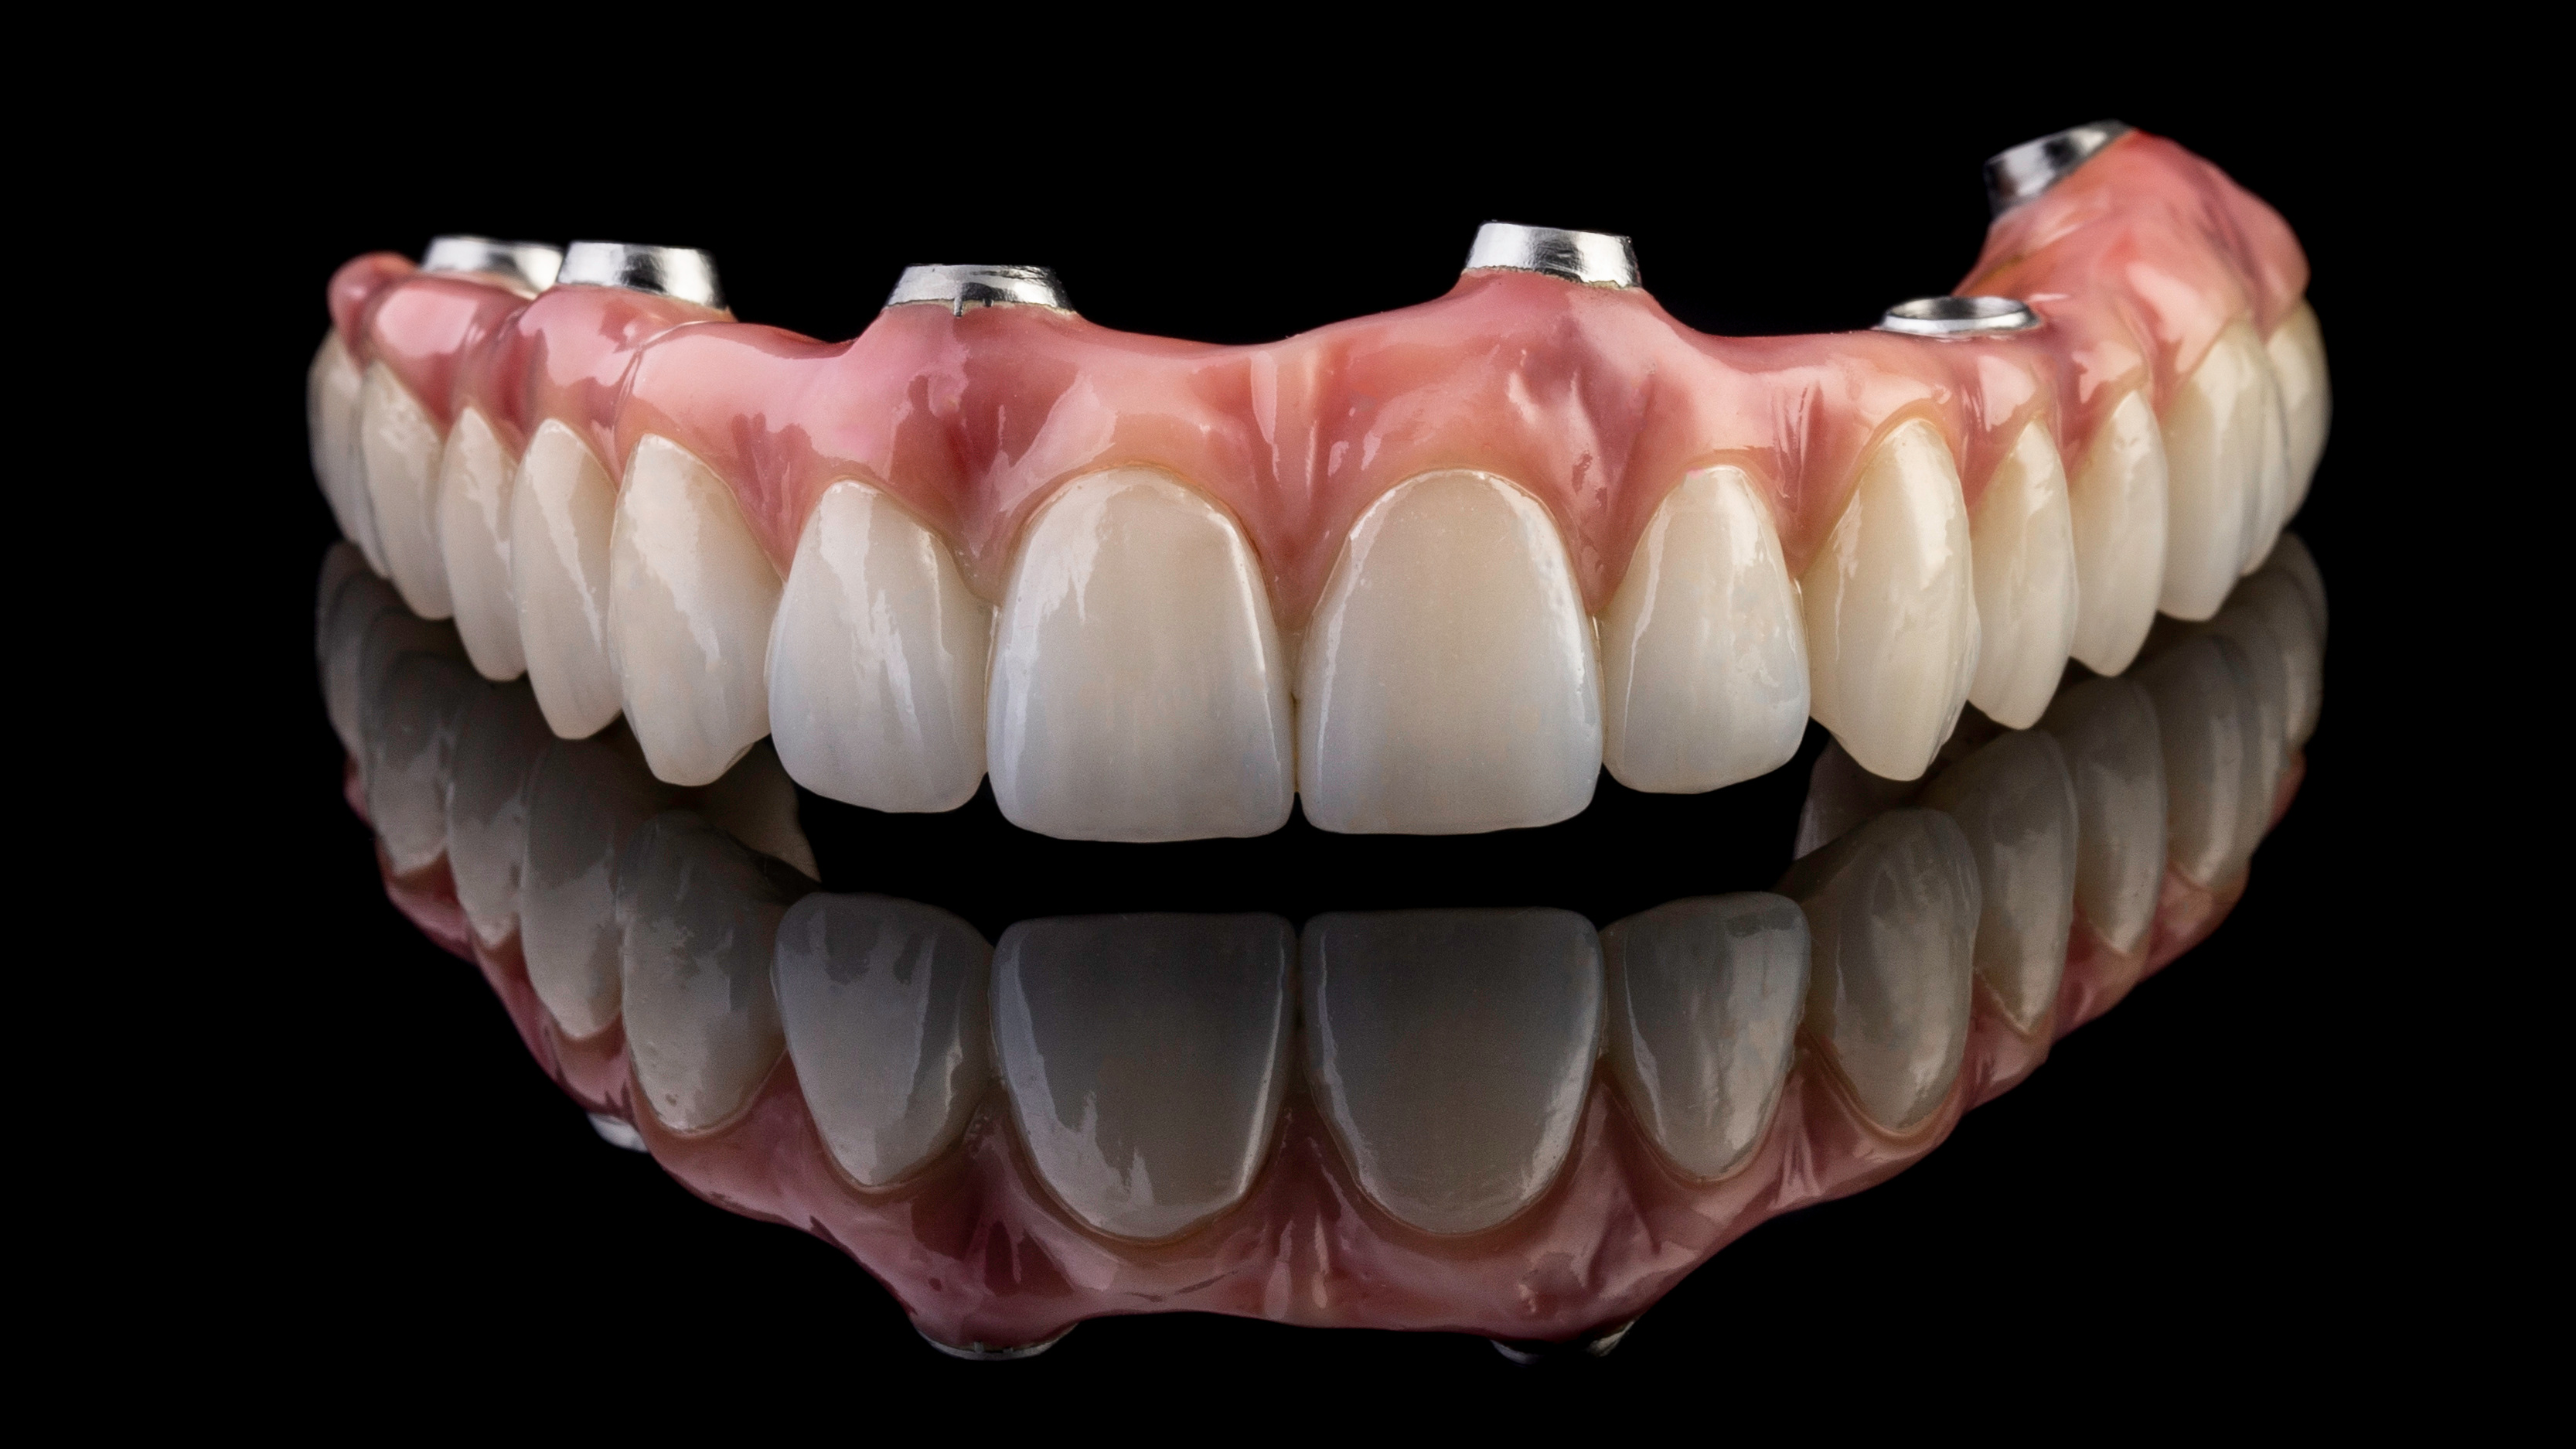
When significant bone has been lost in the area, the restoration needs to replace not just the tooth but also part of the bony ridge that’s missing. An FP-3 uses pink-colored material to replicate the gum tissue in the area of the defect, combined with the white tooth portion above.

This is why doing bone grafts immediately after an extraction is so critically important, especially in the anterior teeth — the esthetic zone. Preserving bone height at the time of extraction keeps FP-1 and FP-2 options available. Once bone is lost, the restoration has to compensate for what’s missing, which adds complexity and can affect the cosmetic outcome.

For patients with a high lip line, the difference between FP-1 and FP-3 can be dramatic. When the gums are visible during smiling and speech, every detail of the restoration — the gum contour, the pink tissue replacement, the transition from restoration to natural tissue — is on display. This is exactly why Dr. Kriston’s pre-surgical esthetic zone analysis is so important: it identifies whether an FP-1, FP-2, or FP-3 is likely based on the available bone and tissue, and sets realistic expectations before surgery begins.

Removable Implant Restorations

These restorations are supported by implants but can be removed by the patient for cleaning or by the dentist for maintenance.
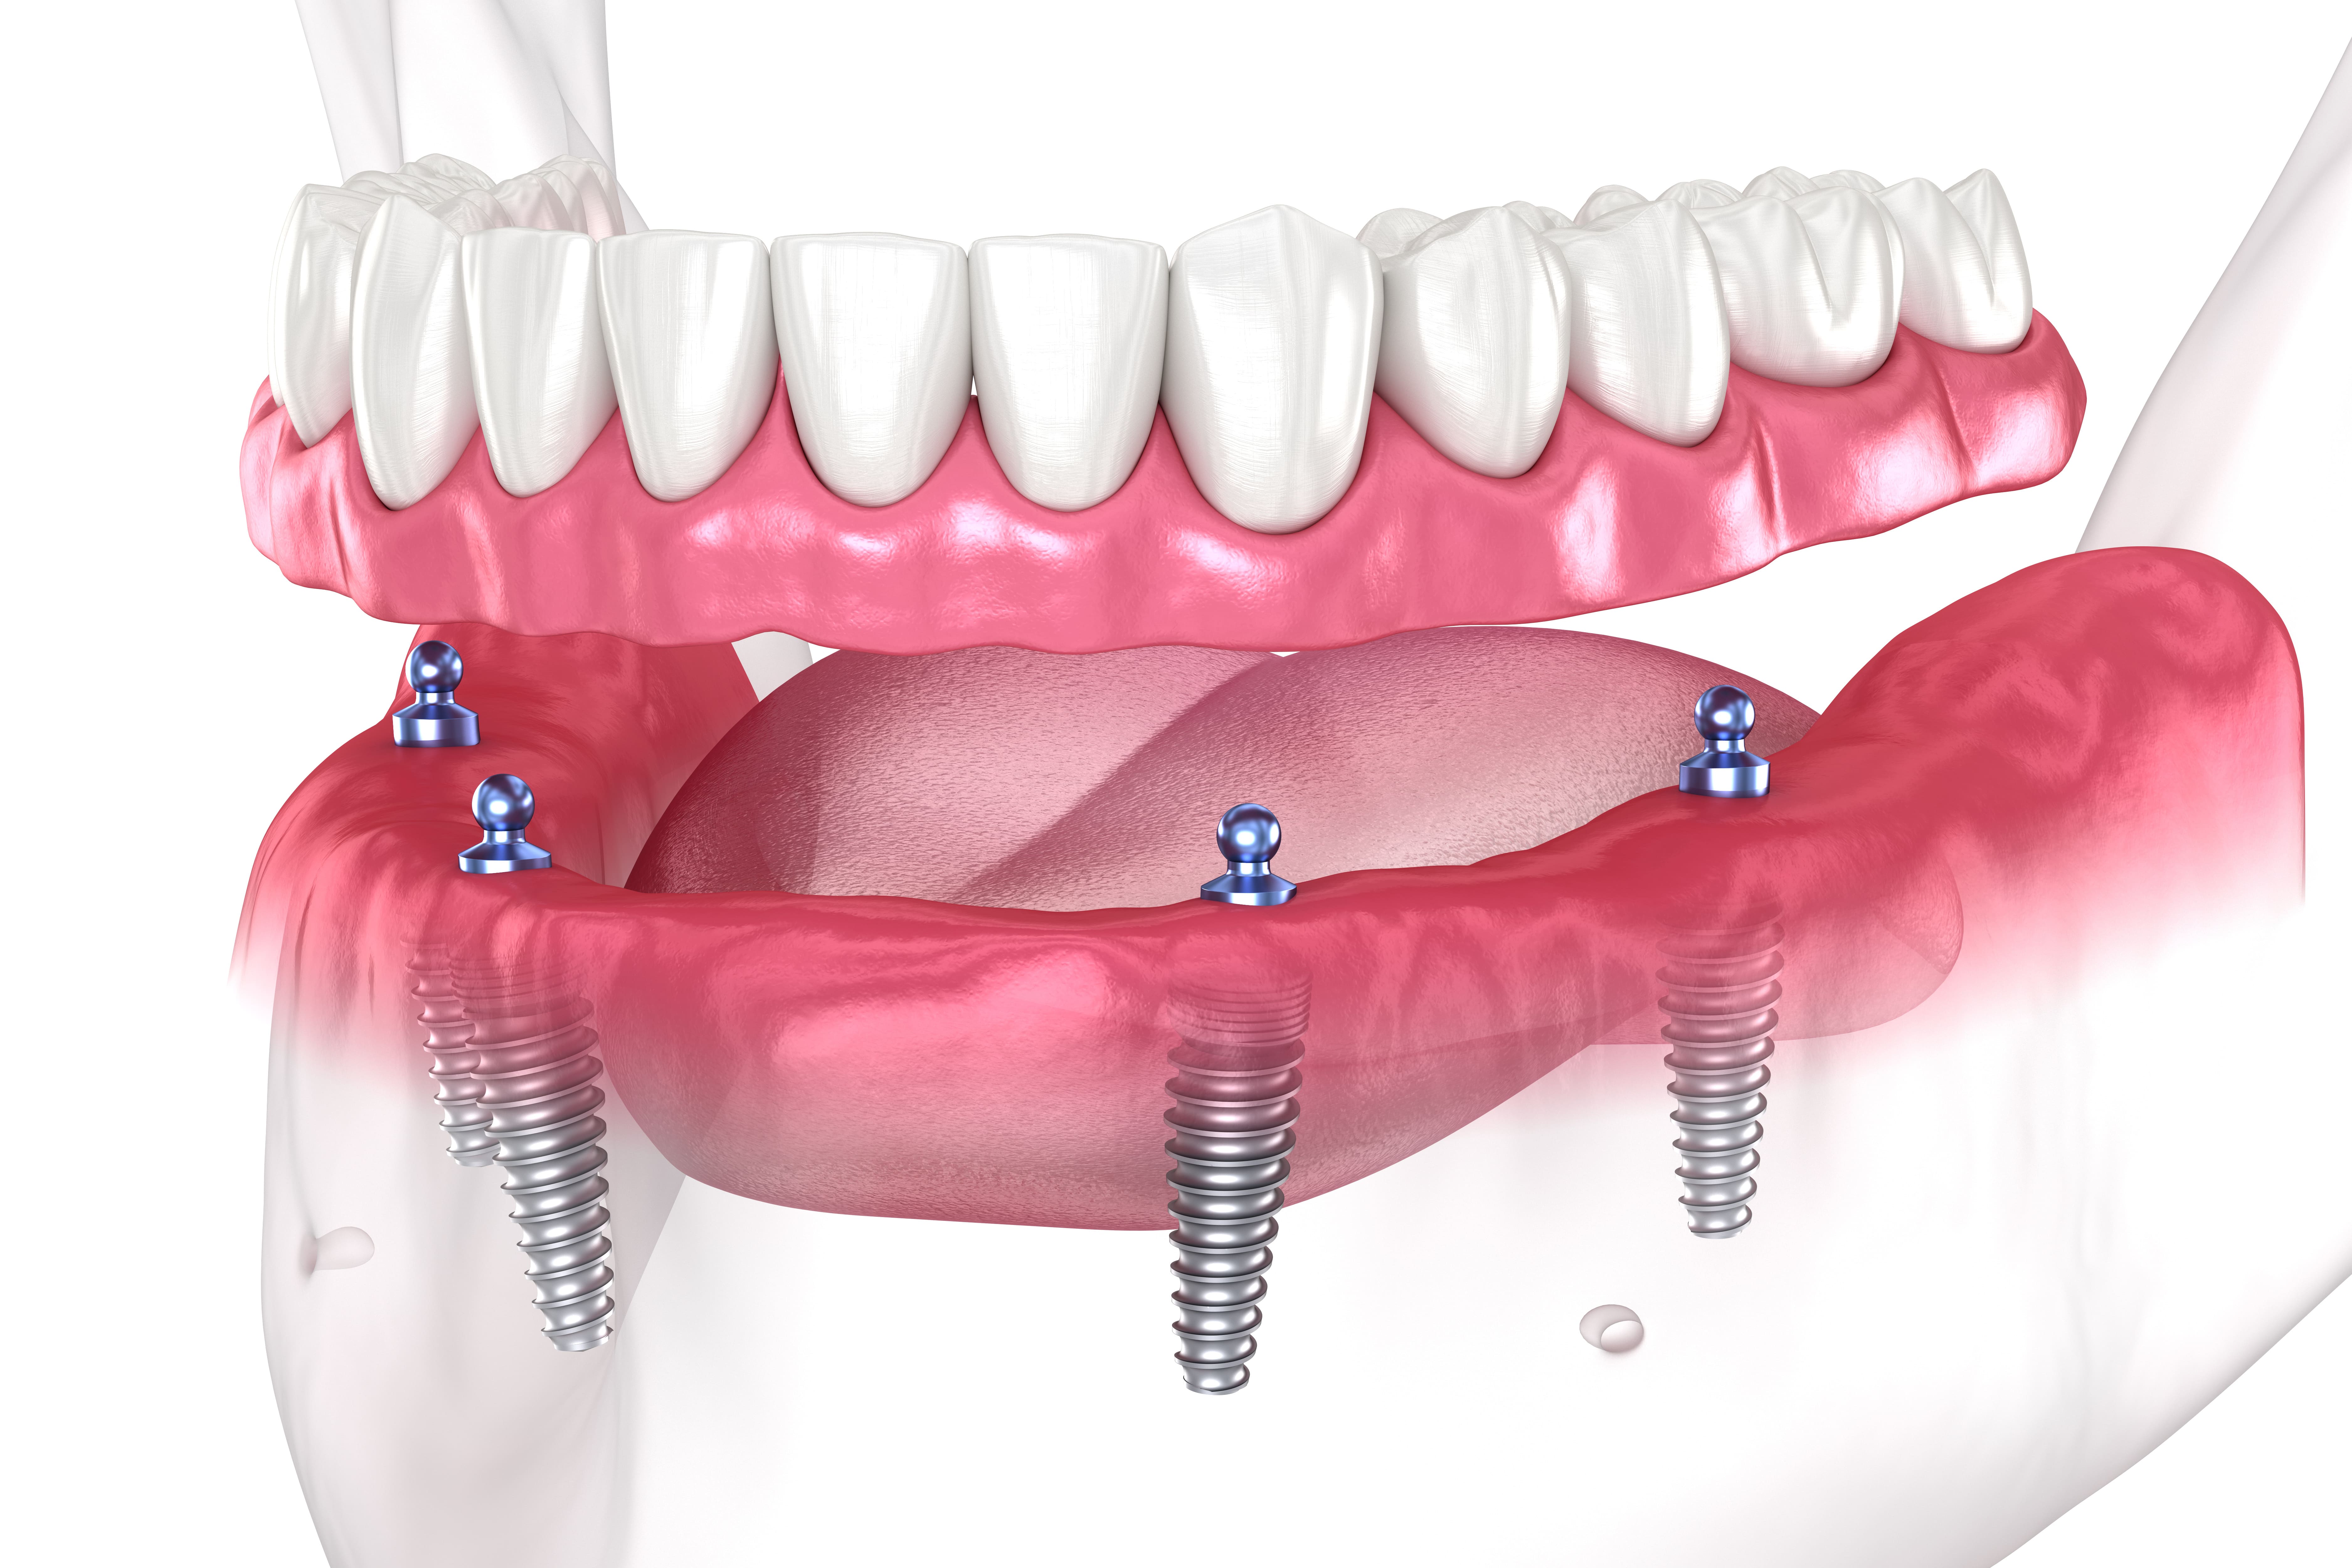
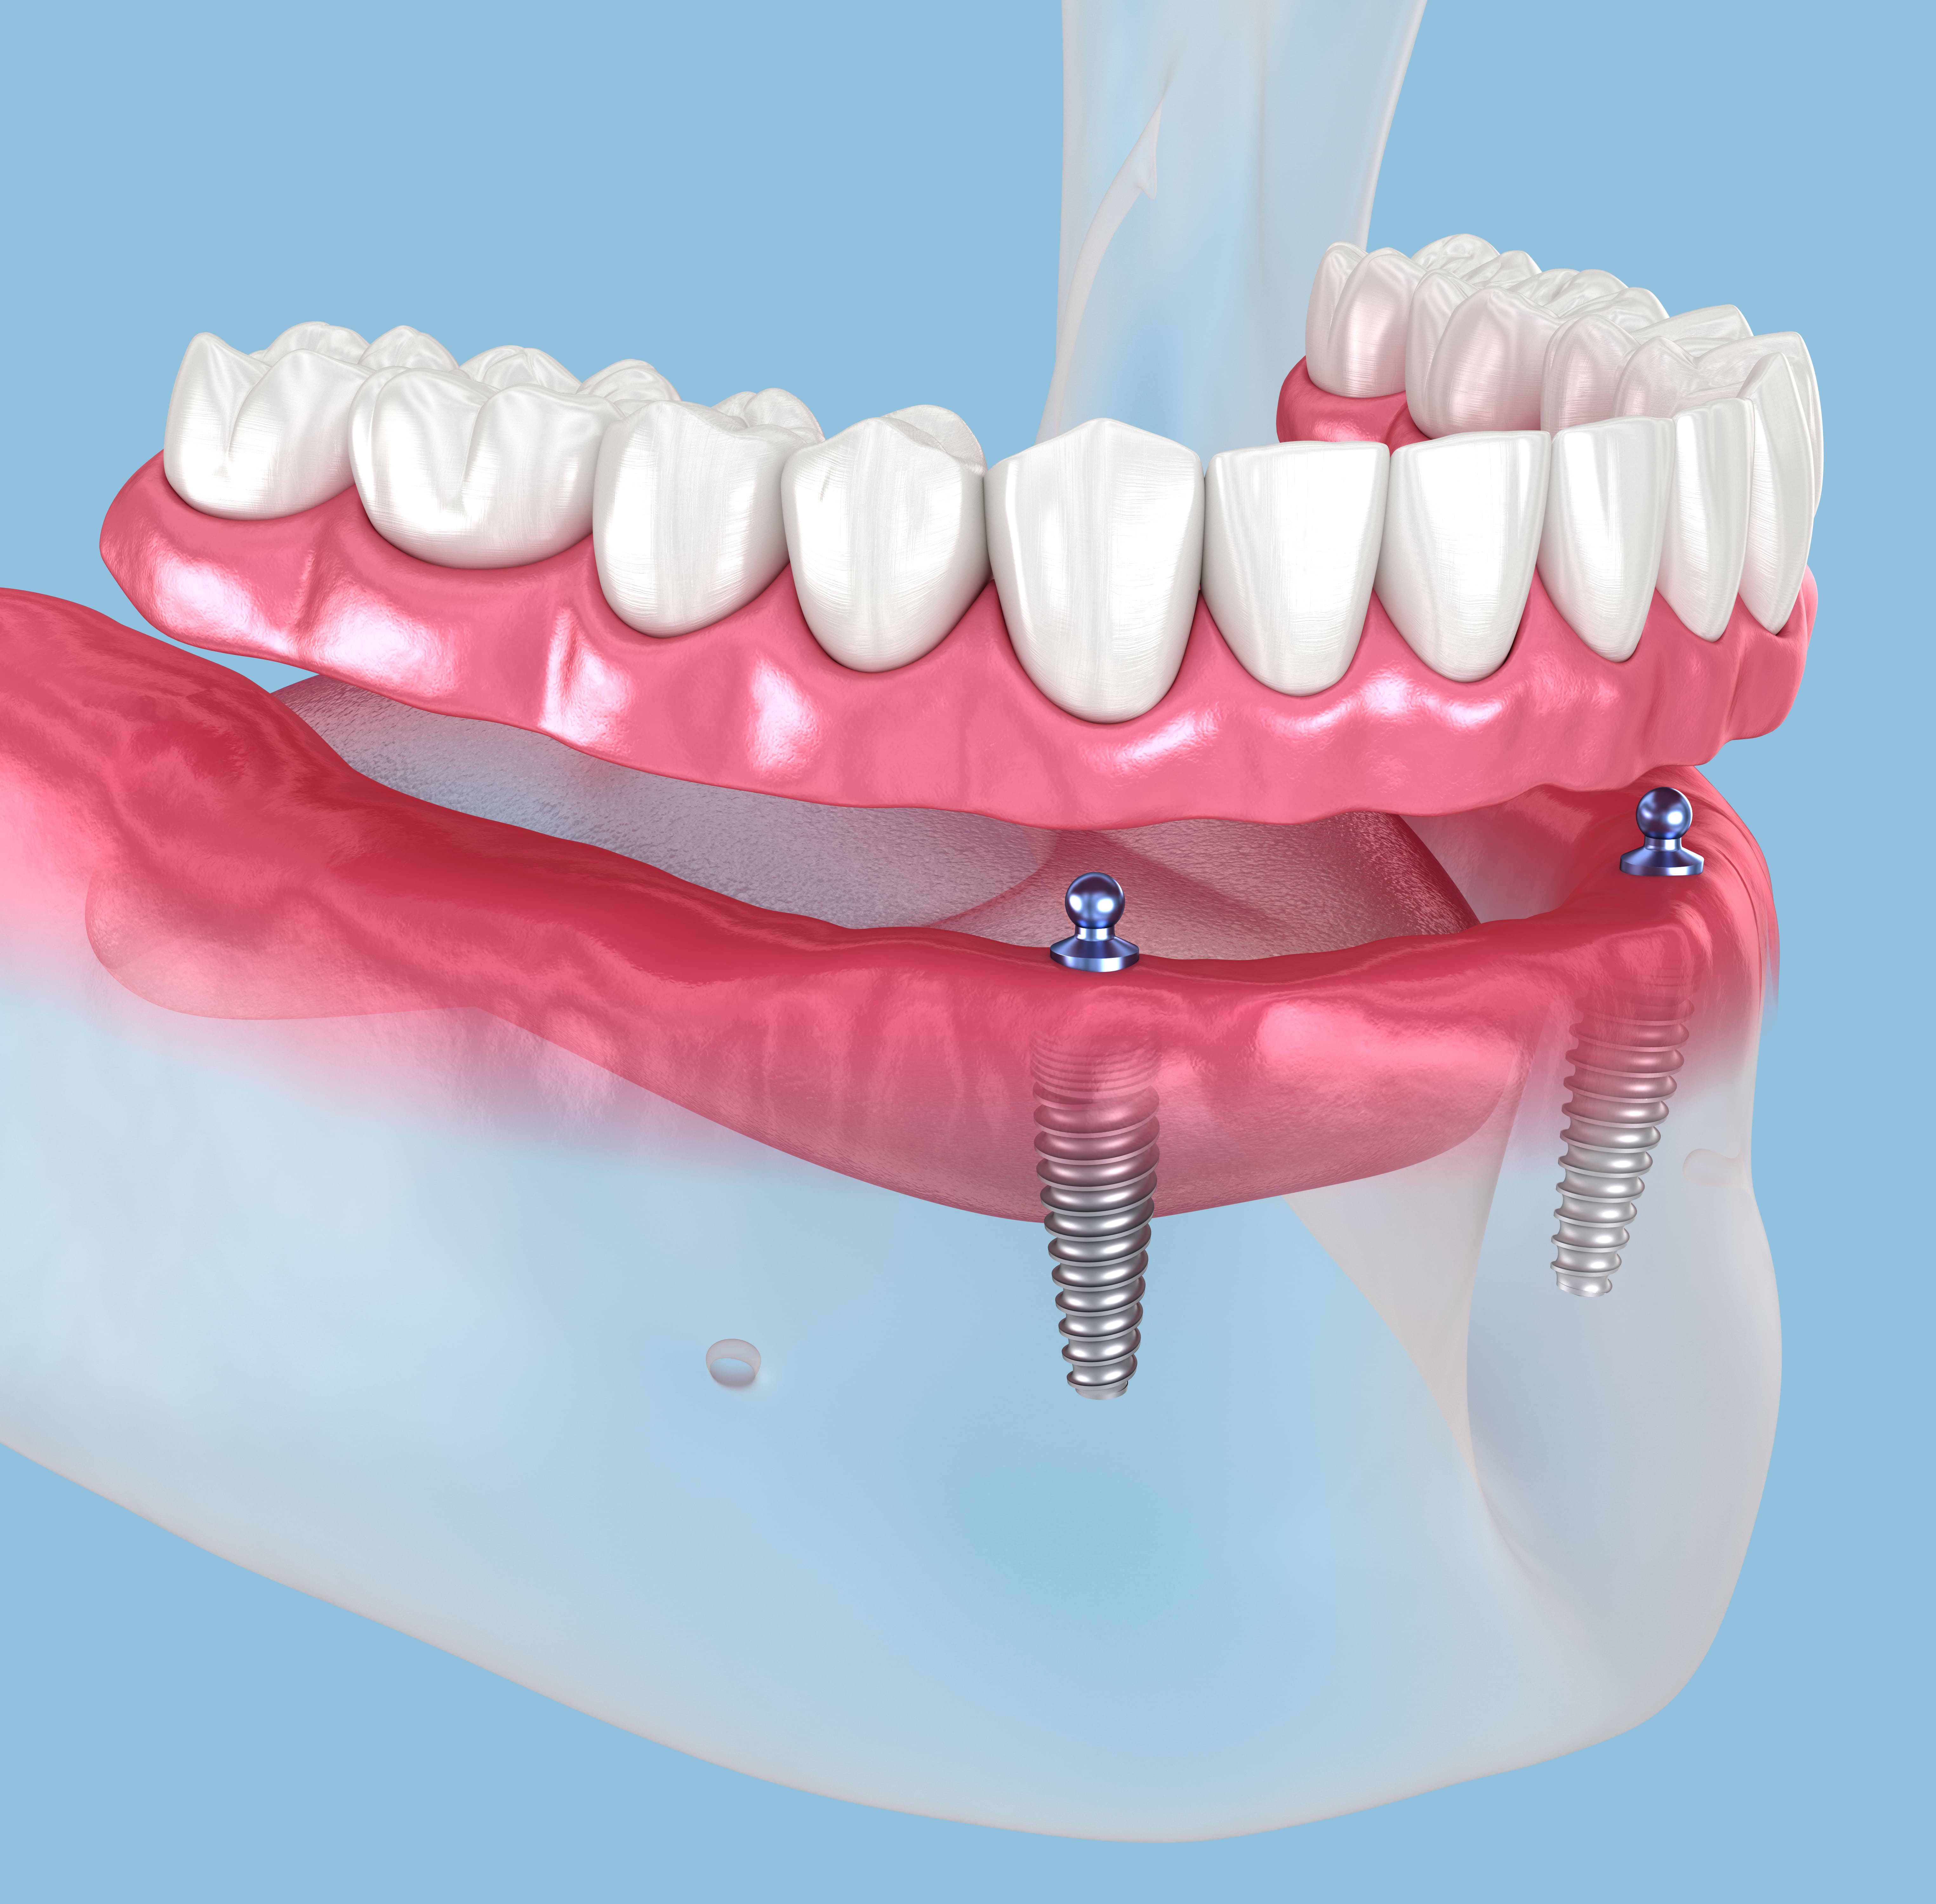
RP-4: Removable Prosthesis, Type 4 — Implant-Supported Only

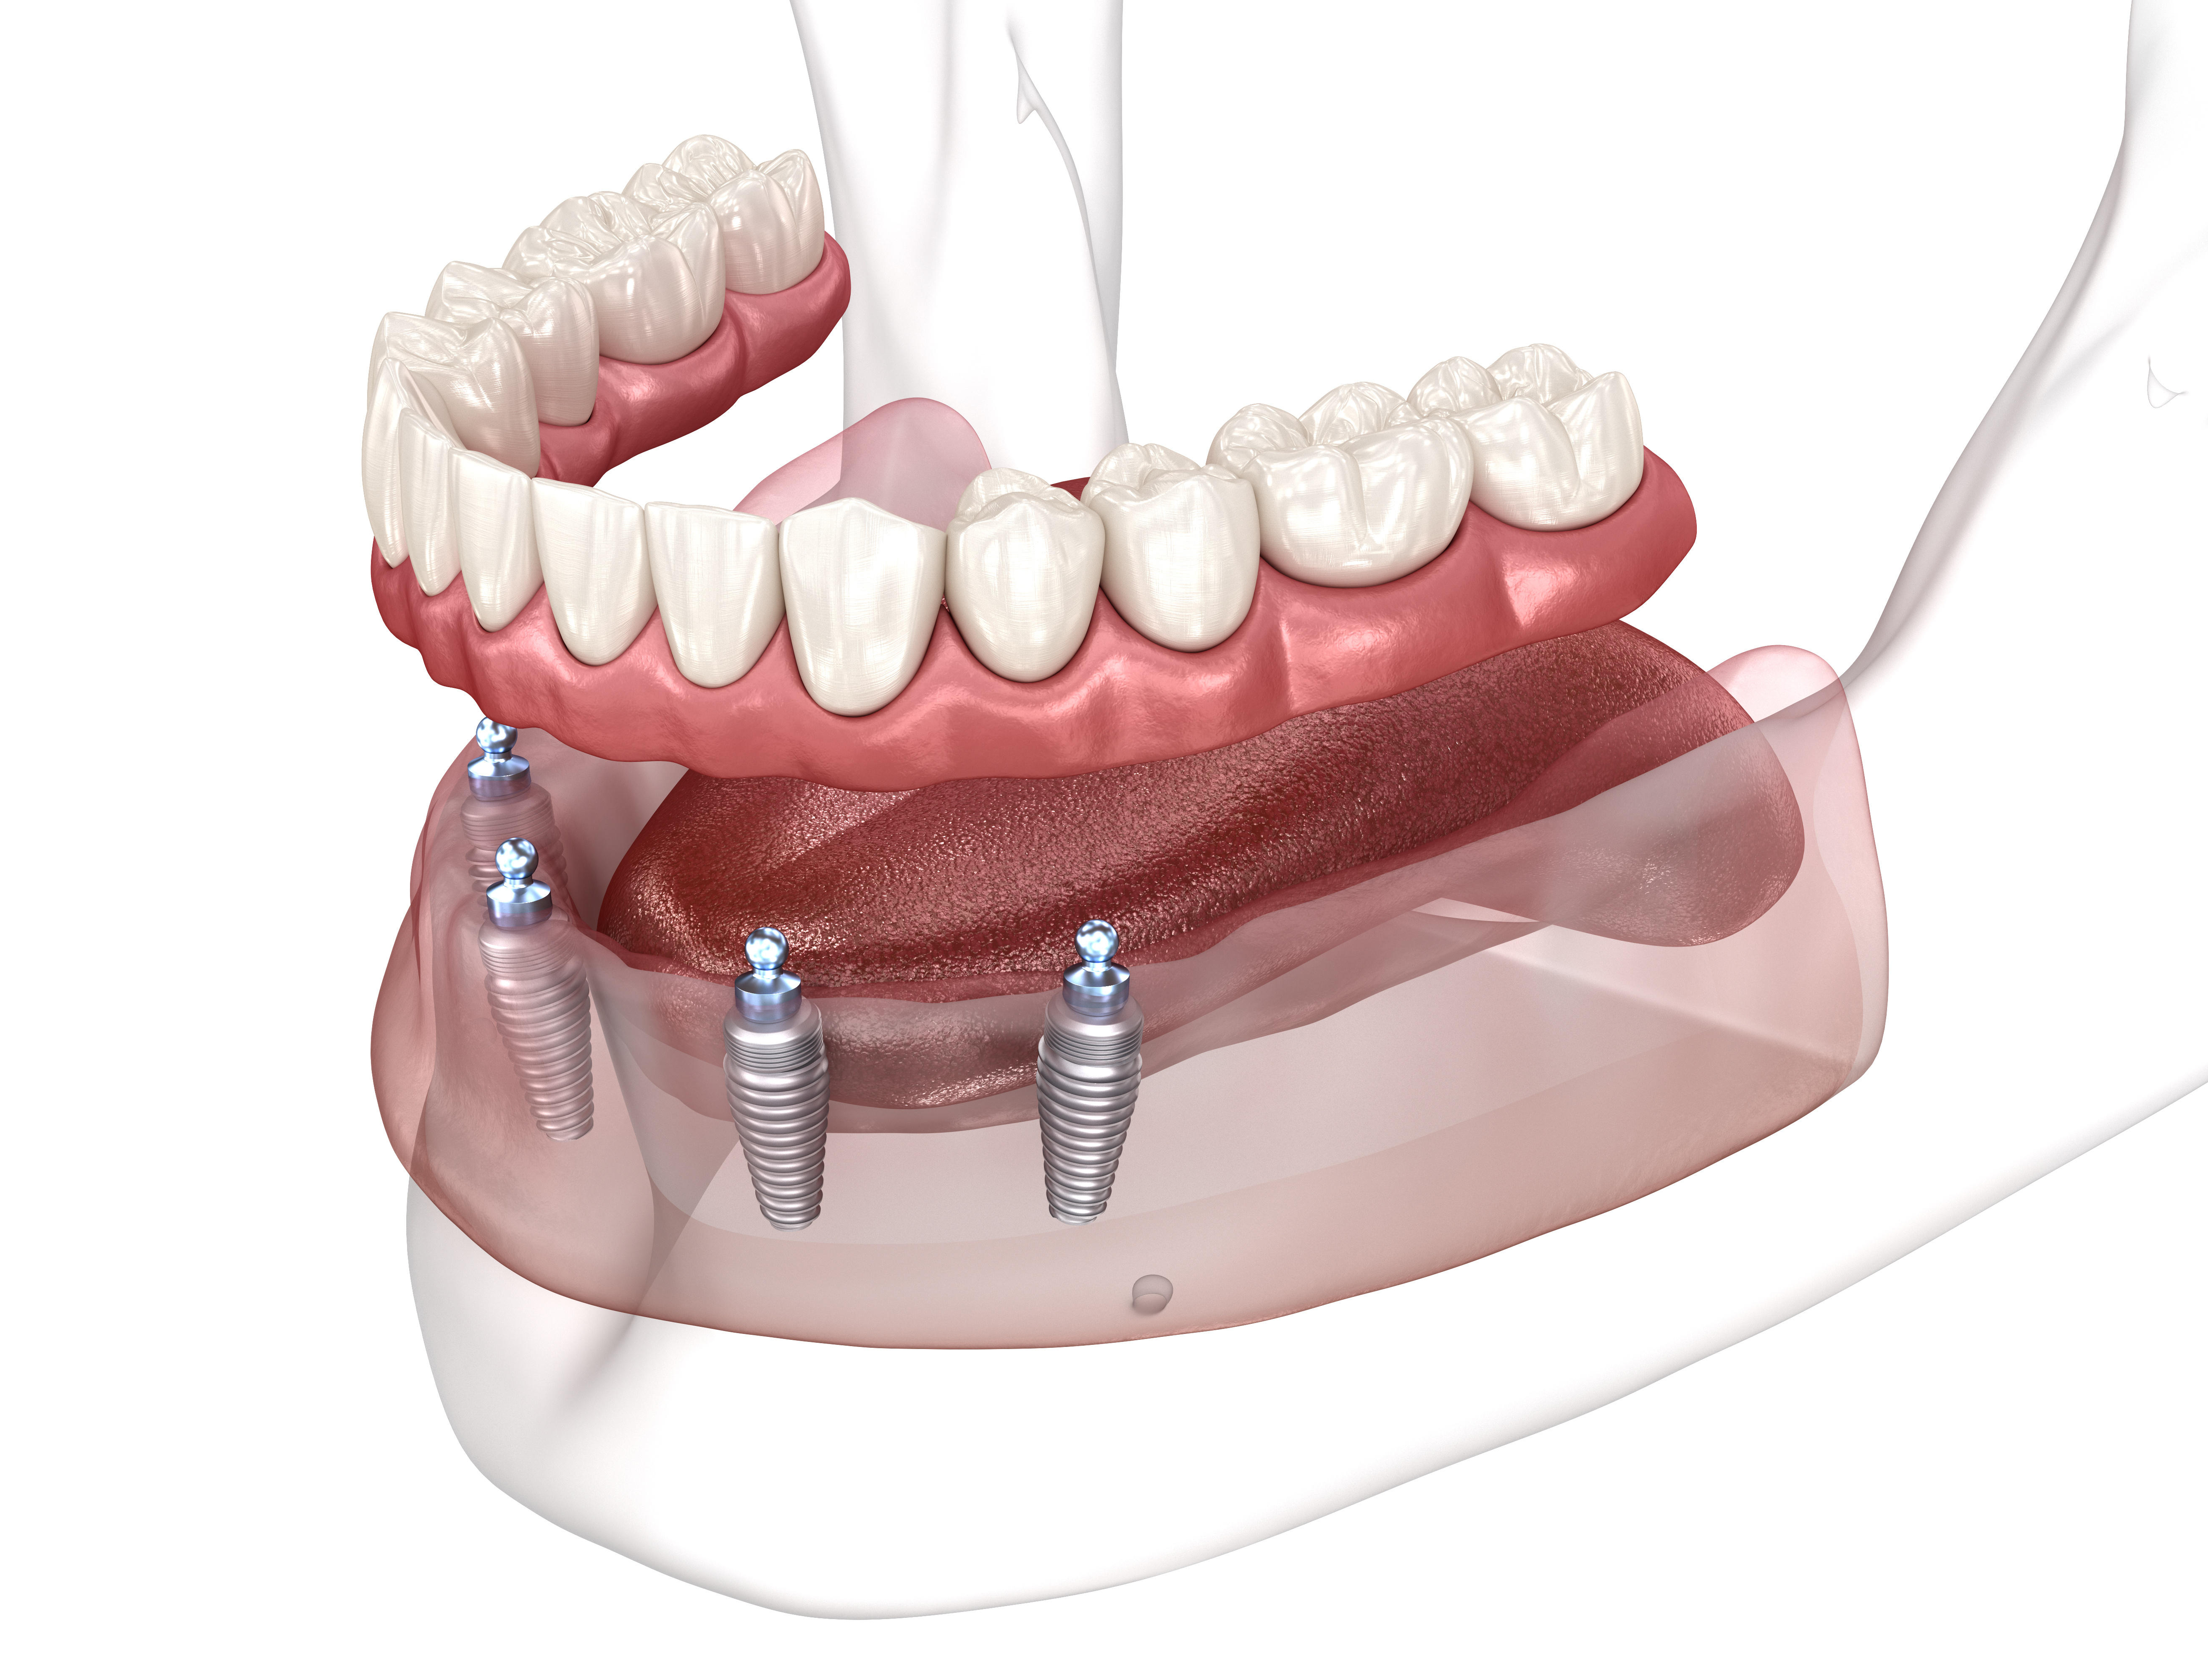
An RP-4 is a denture that is entirely supported by dental implants. It does not rest on the gums at all — the implants carry all the weight and force. This design provides excellent stability and a more natural feel because the prosthesis isn’t pressing against the tissue. RP-4 prostheses are removable by the wearer for cleaning.

RP-5: Removable Prosthesis, Type 5 — Implant and Tissue Supported

An RP-5 is a denture supported by both the implants and the gum tissue. The implants provide retention (keeping the denture from moving), while the tissue helps distribute some of the chewing forces. This design typically requires fewer implants than an RP-4, making it a more affordable option while still providing dramatically better stability than a conventional denture.

Implant Restoration Classification at a Glance

Type Category What It Replaces Best When
FP-1 Fixed Crown only (enamel) Bone and gums well-preserved
FP-2 Fixed Crown + partial root (elongated, all white) Moderate bone loss
FP-3 Fixed Crown + root + ridge defect (white + pink) Significant bone loss
RP-4 Removable Full arch, implant-supported only Enough implants for full support
RP-5 Removable Full arch, implant + tissue supported Fewer implants, budget-conscious

Why Bone Grafting at Extraction Matters for Your Implant Restoration

You’ve now seen how the classification of your implant restoration — FP-1 vs. FP-2 vs. FP-3 — depends directly on how much bone is available at the implant site. This is the connection between what happens at the time of extraction and what your final smile looks like years later.

When Dr. Kriston performs an atraumatic extraction with bone grafting, he’s not just preparing the site for an implant. He’s preserving your options for the most cosmetically ideal restoration. A well-grafted extraction site maintains the bone height and volume that makes an FP-1 (crown-only replacement) possible — the most natural-looking result.

Without bone grafting, the bone at the extraction site begins to shrink immediately. Within months, enough bone can be lost that the only viable restoration option becomes an FP-2 or FP-3 — which, while functional and still cosmetically acceptable, can’t achieve the same seamless, natural look as an FP-1.

This is one of the core reasons Dr. Kriston advocates for having your restorative dentist involved from the very beginning of the implant journey — from the extraction through the final restoration. When the doctor who will design your smile is also the one planning your extraction and bone graft, every step is coordinated toward the best possible cosmetic outcome.
Restorative-Driven Implant Planning

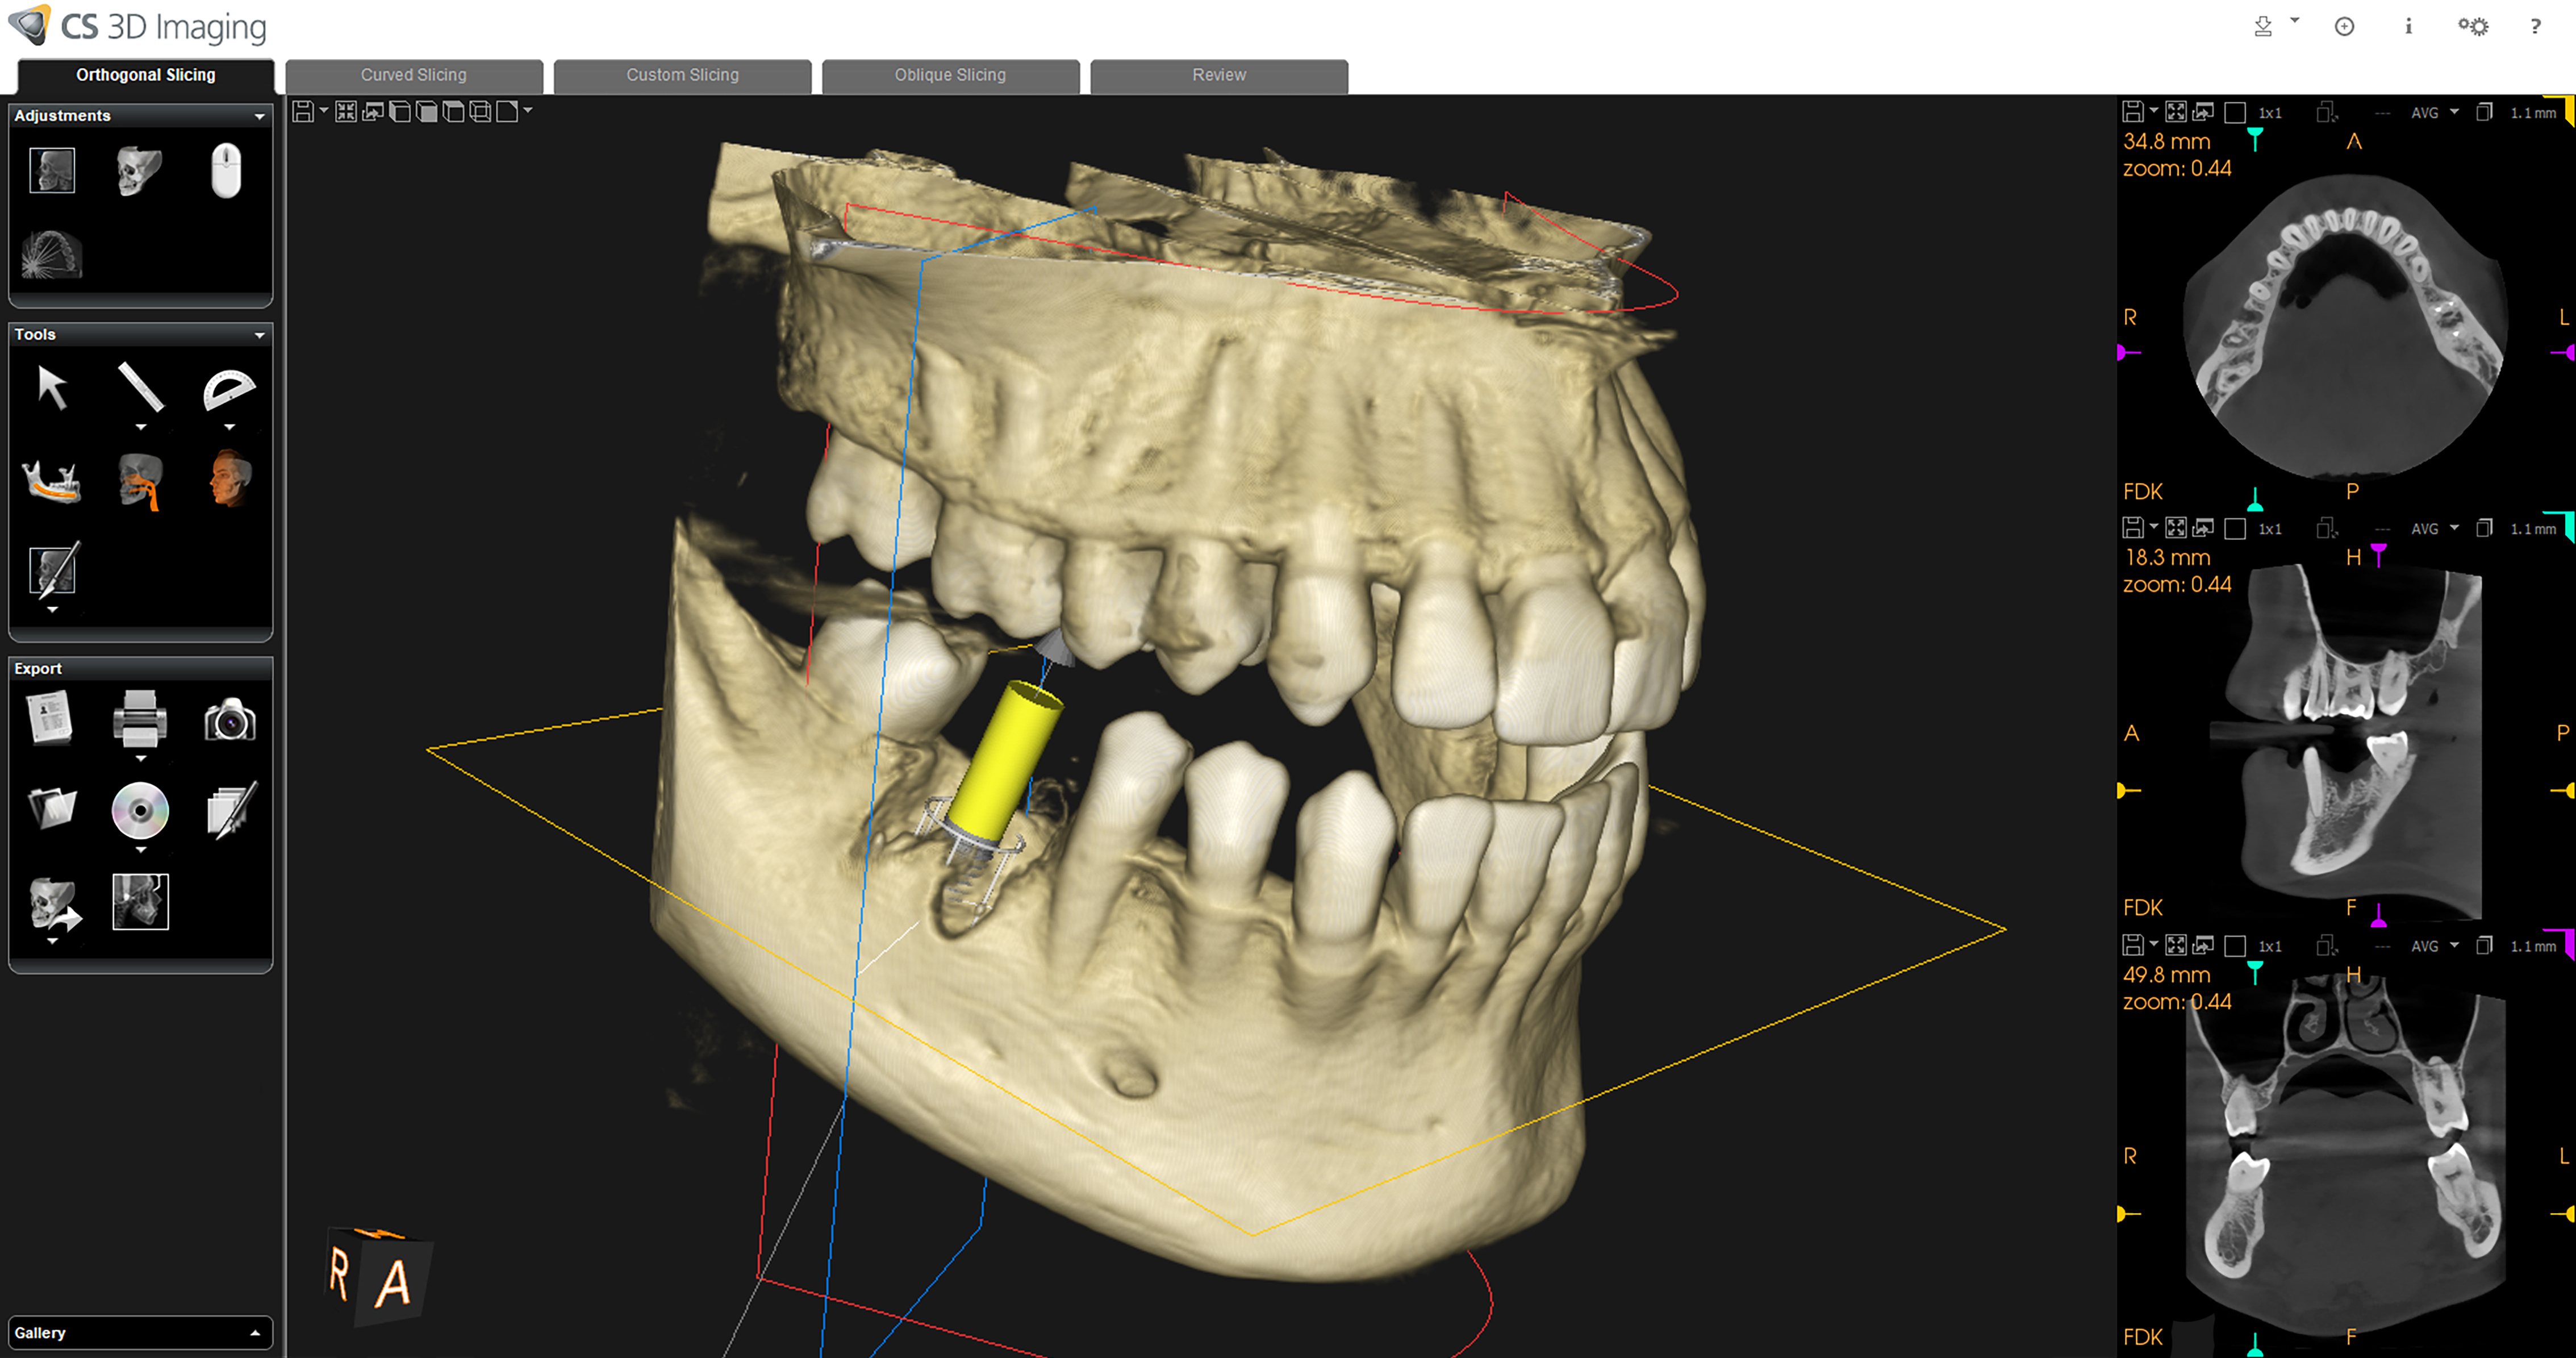
Dr. Kriston uses a restorative-driven approach to every implant case. Rather than placing the implant first and designing the restoration around wherever it ends up, he reverses the process: design the ideal restoration first, then determine where the implant needs to be to support it.

Using our Medit intraoral scanner, Dr. Kriston creates a precise 3D digital model of your mouth and designs the ideal crown, bridge, or prosthesis. That restoration design is then overlaid onto your Carestream 3D CBCT scan to determine the exact implant position, angle, and depth needed to support it. The result is a surgical plan where the implant serves the restoration — not the other way around.

This approach is especially critical in the esthetic zone, where even a millimeter of misposition can affect the emergence profile of the restoration through the gum tissue, the symmetry with adjacent teeth, and the overall cosmetic result.

The Implant Restoration Process

The implant journey typically unfolds in two stages:

01

Implant Placement

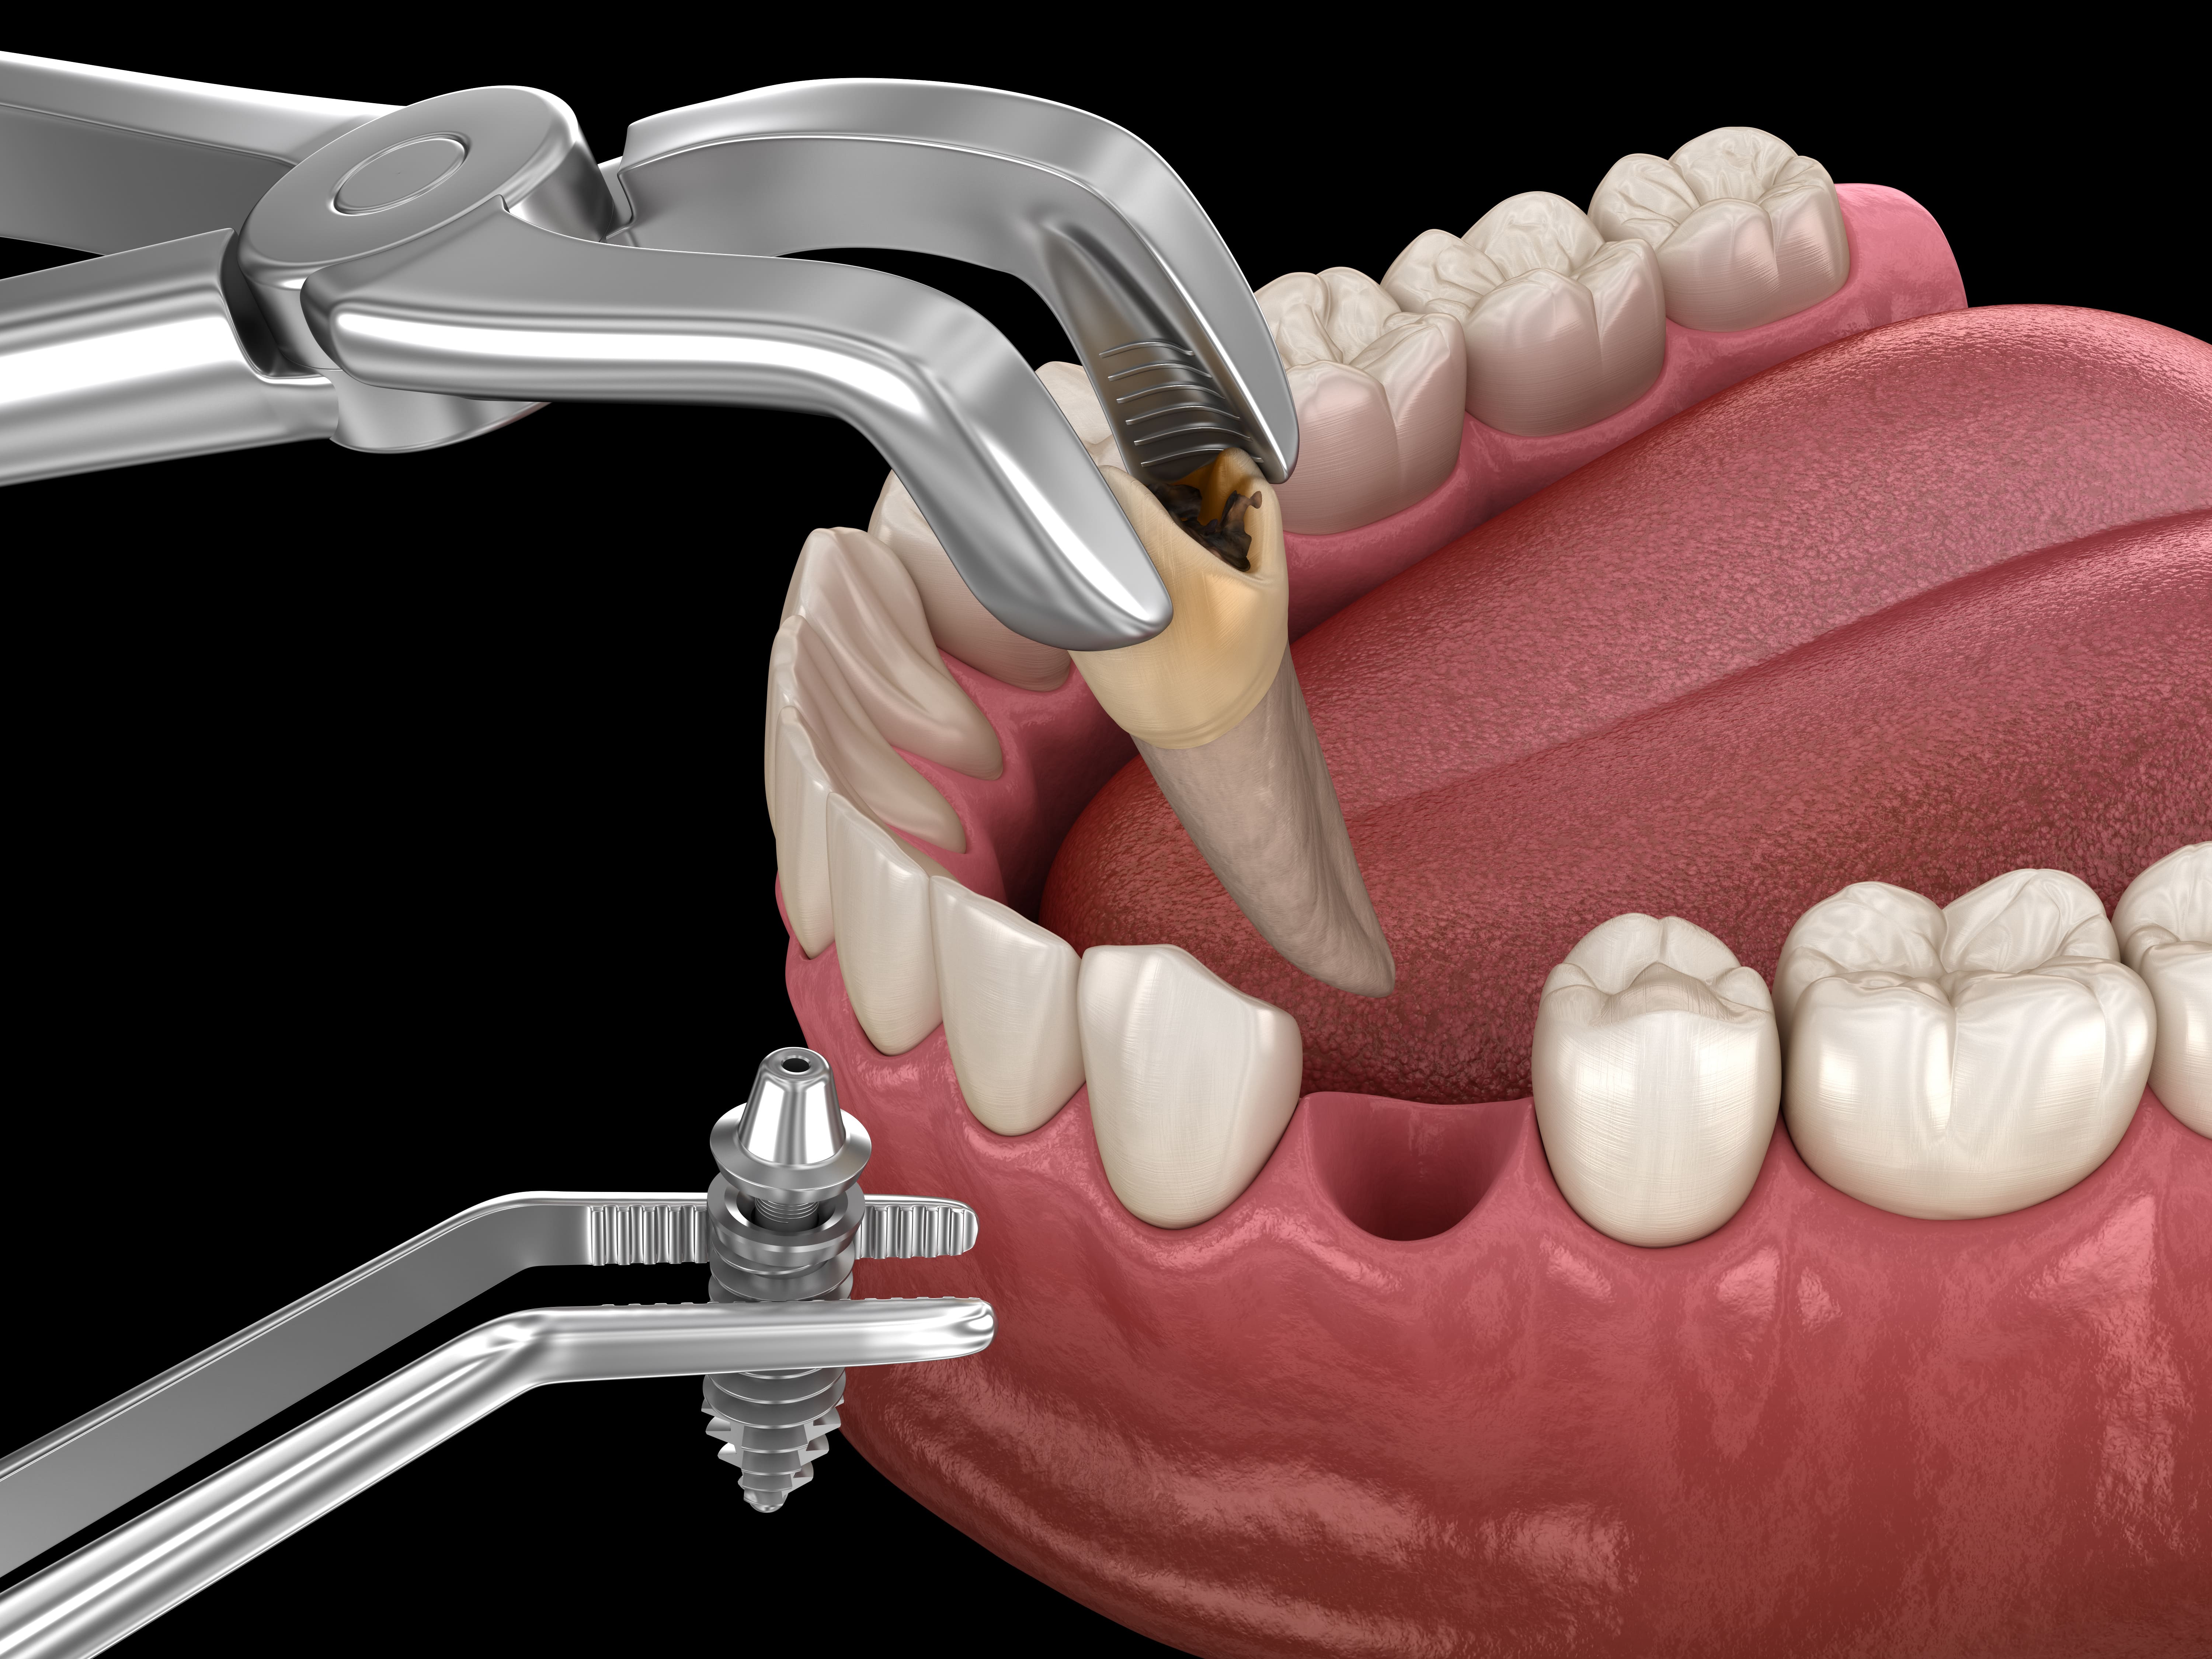
The implant is placed into the jawbone using 3D imaging and precise surgical measurements to ensure adequate bone surrounds the implant. A temporary appliance with a replacement tooth is provided so you never go without a smile while healing. The bone needs two to three months to fuse with the titanium implant — this healing time is essential for long-term success. It also allows the gums to mature so they don’t recede once the final restoration is placed.

Depending on the case, implant placement may be performed by Dr. Kriston or by one of our trusted oral surgery partners. Either way, the surgical plan originates here — guided by Dr. Kriston’s restorative-driven design and often executed using a computer-designed surgical guide for pinpoint accuracy.

02

Restoration

Once the implant has fully integrated with the bone, Dr. Kriston takes a precise digital impression using our Medit scanner. He selects and customizes the abutment (gold-tone anodized titanium, zirconia, or standard titanium depending on the esthetic requirements), designs the crown, bridge, or prosthesis, and works with his laboratory to create a restoration that matches your natural teeth in every detail. The final placement of the restoration occurs in as little as two weeks after the impression.

This two-stage process also has a practical benefit: it allows the expense to be divided over time, making the investment in dental implants more manageable.
What About Same-Day Implant Teeth?

You may have heard about “same-day implants” or “immediate load” procedures where a tooth is placed on the implant the same day it’s surgically inserted. Dr. Kriston wants to be transparent about this:

Same-day temporary teeth are possible in certain cases. A provisional (temporary) crown or bridge can be attached to the implant on the day of surgery to maintain your appearance. However, full chewing forces should rarely be placed on an implant right away. Letting the bone grow and mature around the implant for two to three months is what assures its long-term success.

It also allows the gum tissue to stabilize. If a permanent restoration is placed too soon, the gums may still be settling — and recession after the final restoration is placed can create cosmetic problems and expose the implant margin. Patience during the healing phase protects both the function and the beauty of the final result.

Types of Implant Restorations We Provide

Single Implant Crowns

A single missing tooth is replaced with one implant and one custom crown. The crown is designed digitally using our Medit scanner, color-matched to your surrounding teeth, and crafted to replicate the exact shape, surface texture, and translucency of a natural tooth. Dr. Kriston pays particular attention to the emergence profile — how the crown transitions through the gum tissue — to ensure a completely natural appearance.

Implant-Supported Bridges

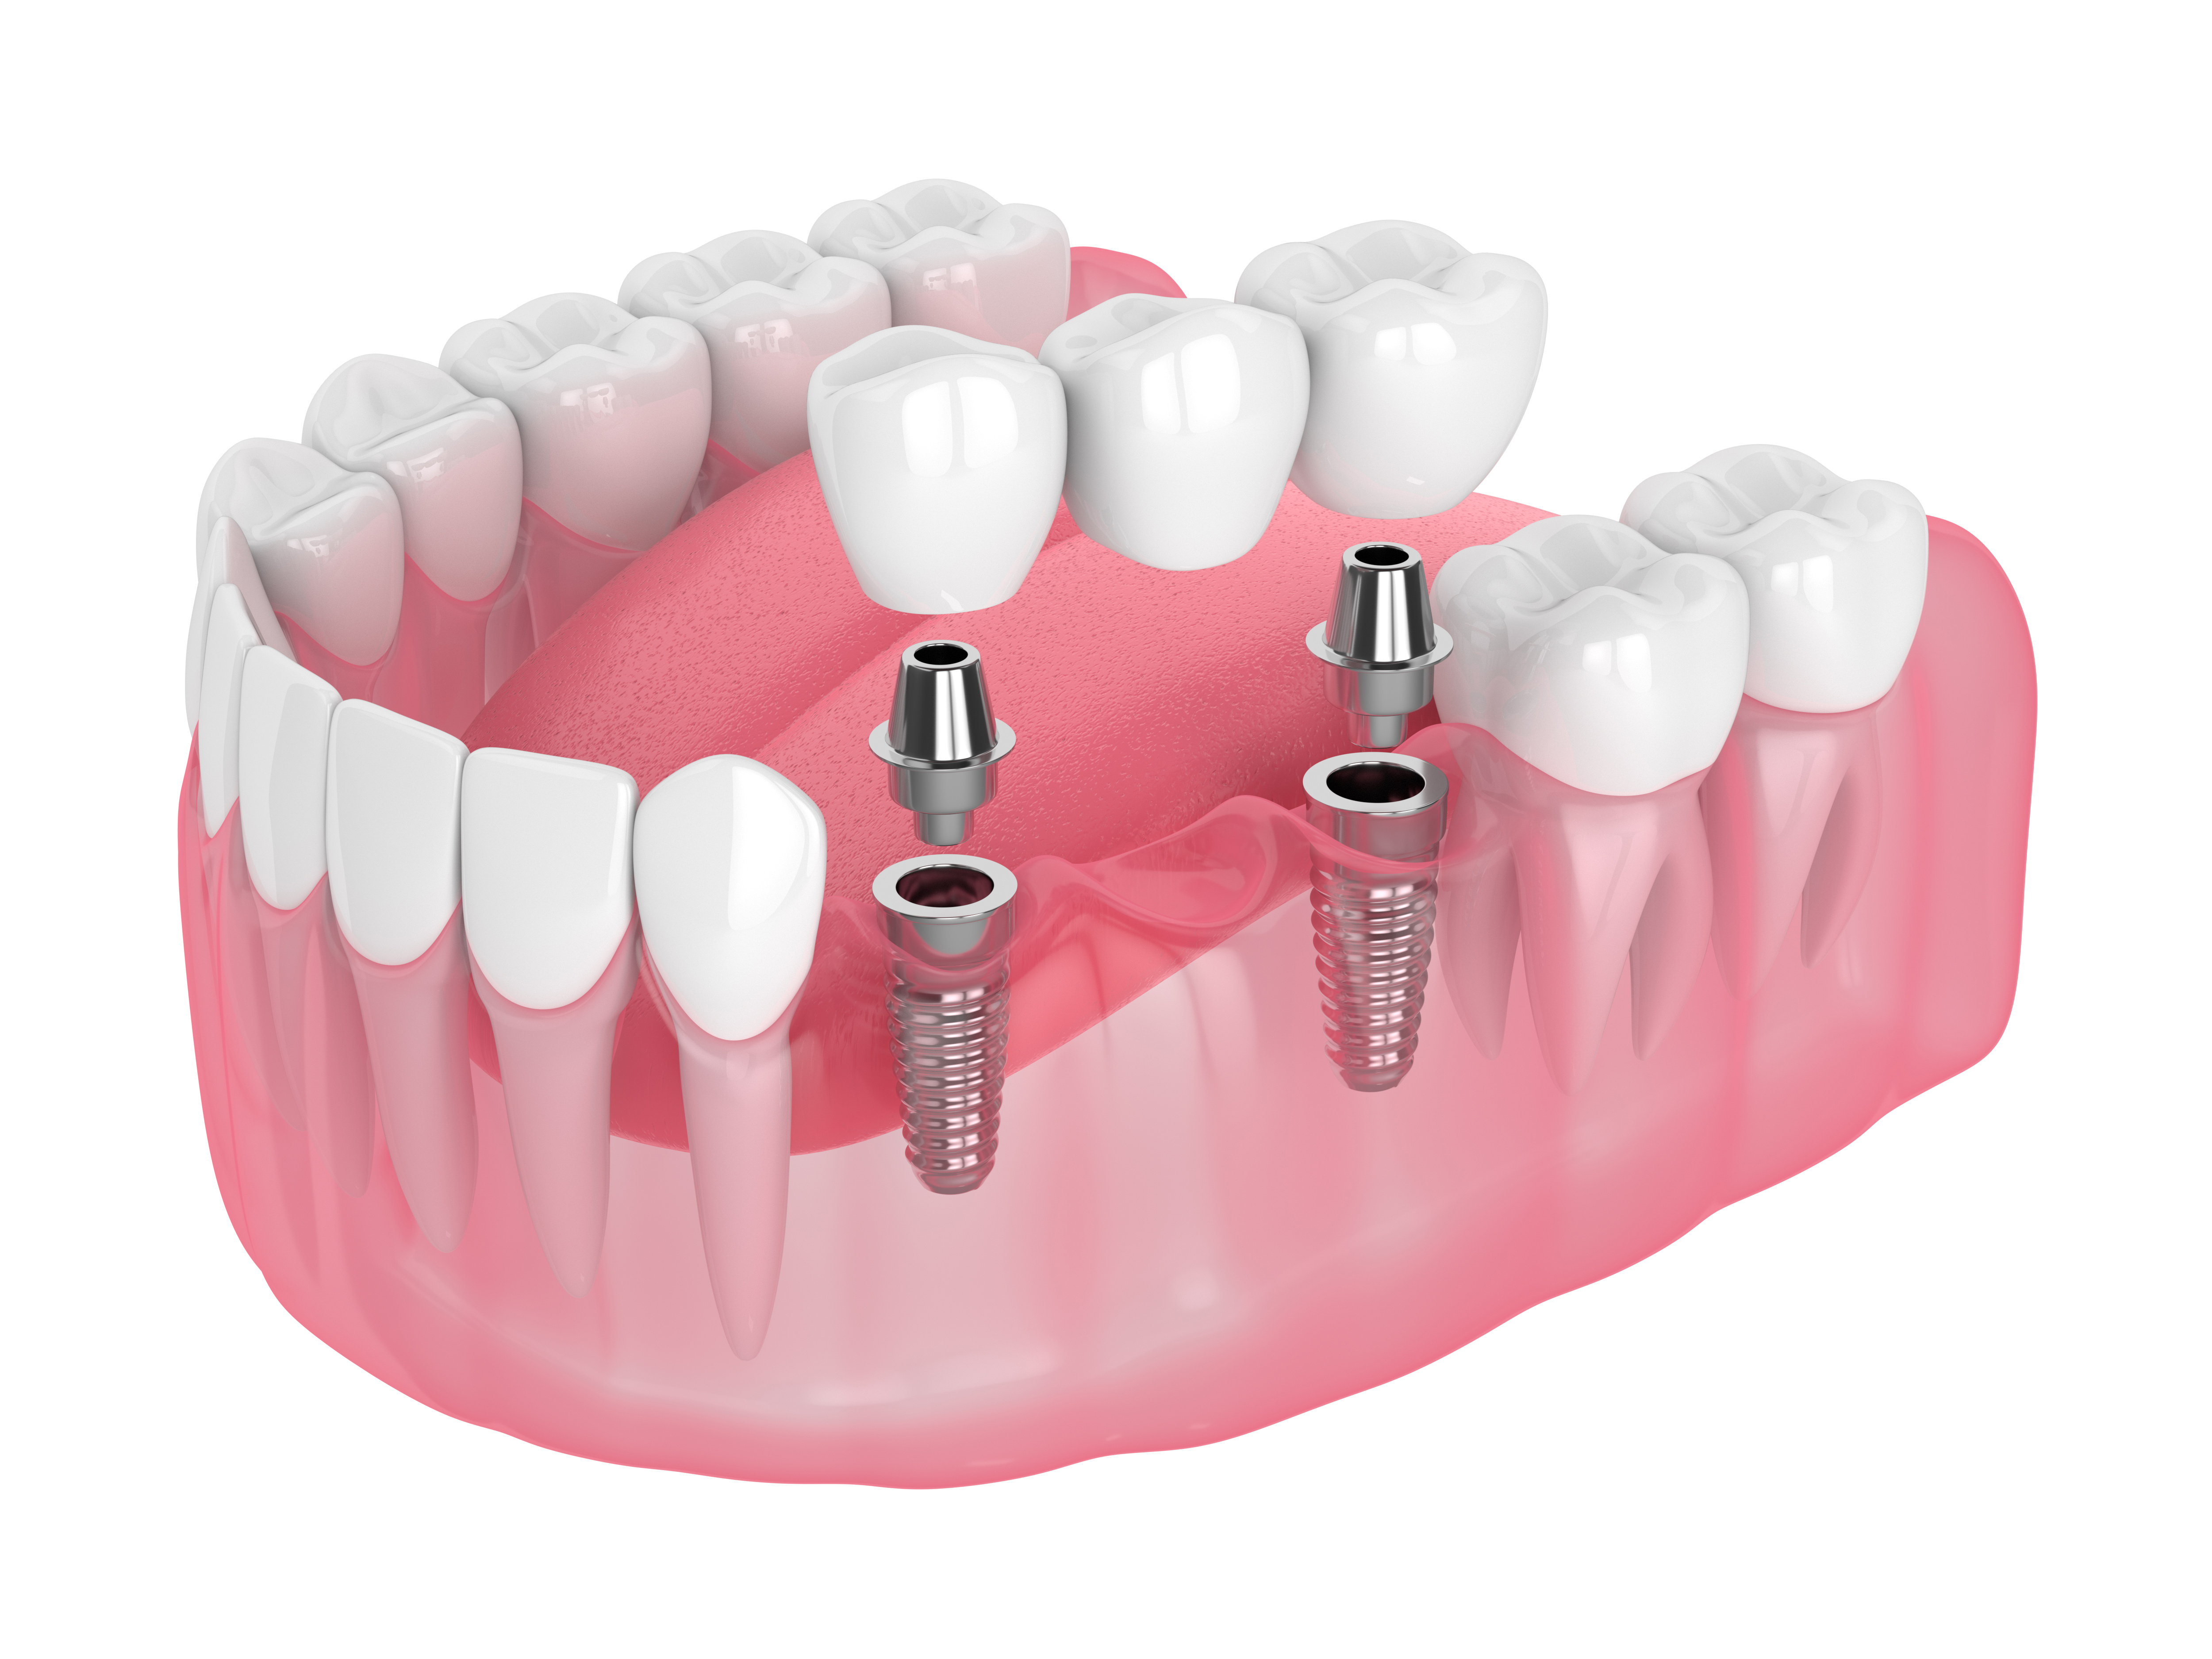
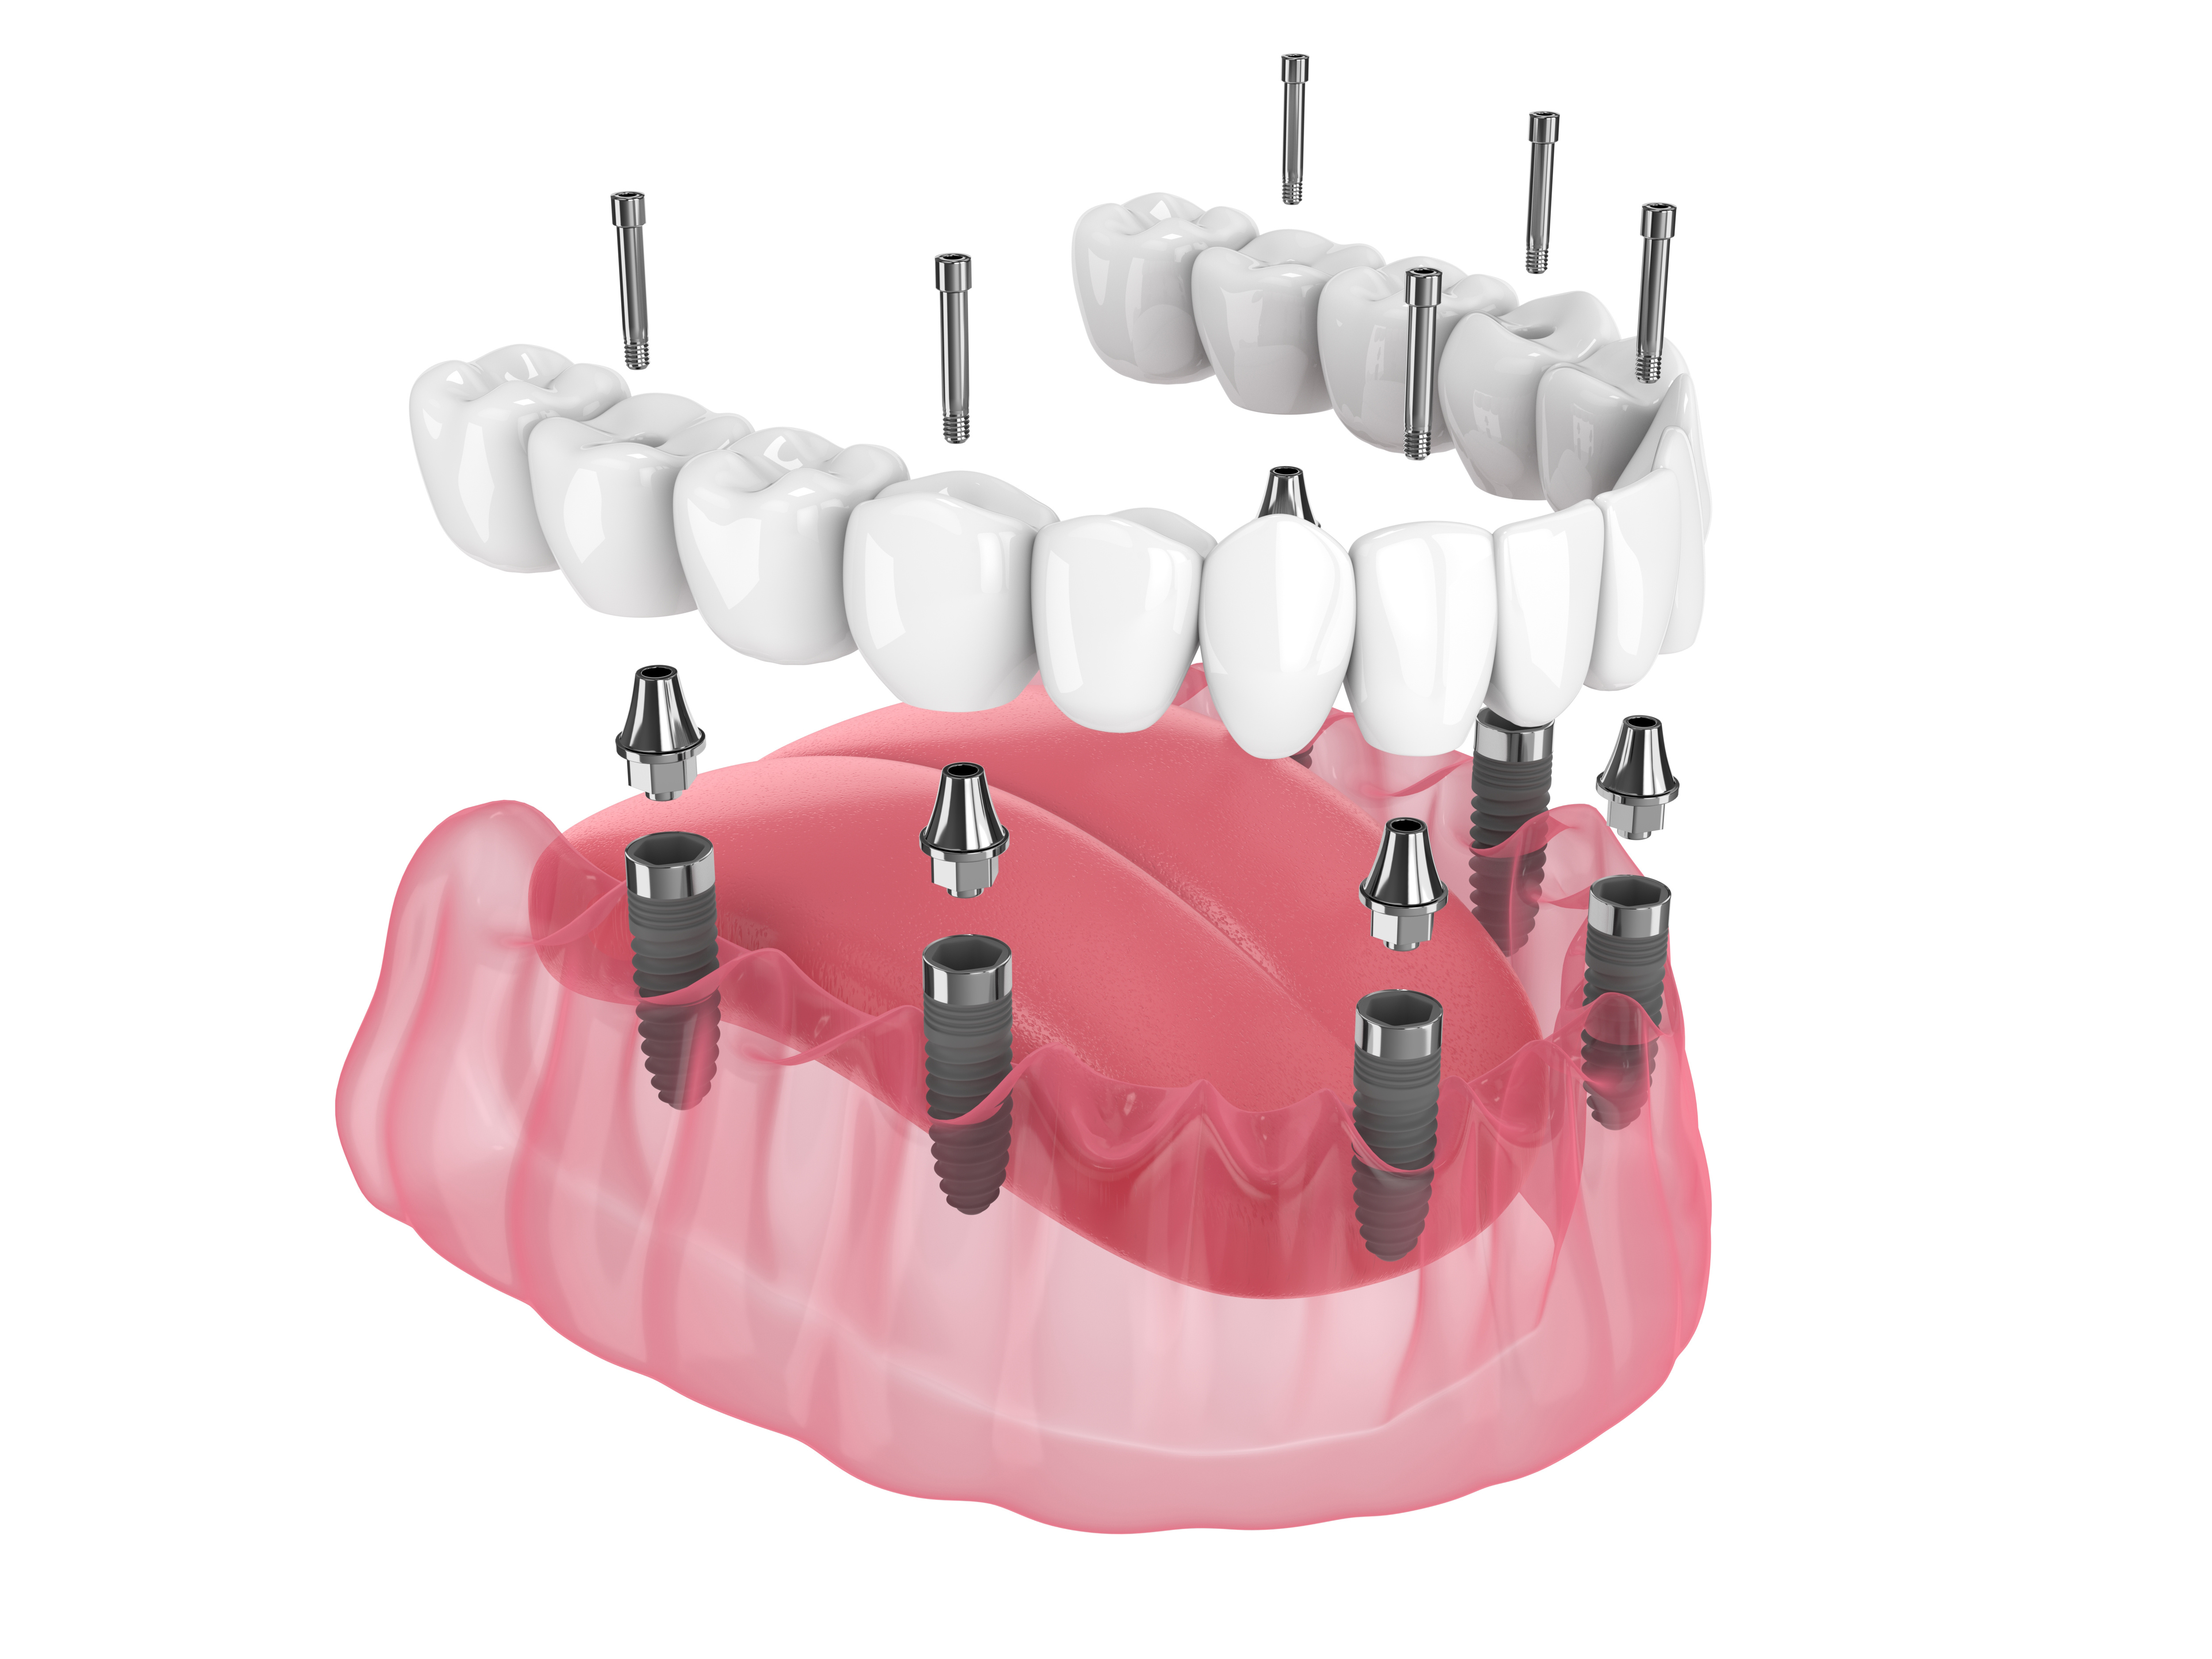
When two or more adjacent teeth are missing, an implant-supported bridge replaces them without affecting healthy neighboring teeth (unlike a traditional bridge, which requires grinding down the adjacent teeth for support). Two implants can support a three-tooth bridge — giving you the function and appearance of three natural teeth with only two surgical sites.

Implant-Supported Dentures

For patients missing most or all of their teeth, implant-supported dentures provide dramatically better stability, comfort, and function than conventional dentures. Dr. Kriston designs both RP-4 (implant-supported only) and RP-5 (implant and tissue supported) prostheses depending on your bone structure, number of implants, and personal goals.

The implant’s extreme bond to bone means a full set of upper or lower teeth can be anchored by as few as four implants — a concept known as All-on-4. Many patients who have worn dentures for years and wish they’d gotten implants sooner are still candidates. Even when bone has shrunk from years of missing teeth, there are techniques and materials to add new bone in the areas needed for implant placement.

Full Mouth Implant Restorations

Dr. Kriston designs full mouth replacement teeth using implants to create the look and feel of natural teeth. His cosmetic dentistry background means every full arch restoration is designed not just for function but for beauty — natural tooth shapes, realistic gum tissue coloring (in FP-3 cases), and proportions that look like you were born with them.

Making Implant Restorations Affordable

Dental implants can be an incredibly affordable way to replace teeth long-term. While the upfront investment is higher than alternatives like bridges or dentures, implants can last a lifetime with proper care — making them the best long-term value for most patients.

The two-stage process naturally divides the expense over time. And the biggest value comes from replacing multiple teeth: investing in just two to four implants can give a denture the secure feel of chewing on solid, permanent teeth.

We offer financing options through CareCredit and work with patients to find a payment plan that makes implant treatment accessible. A beautiful smile and chewing confidently can be life-changing — and it shouldn’t be out of reach.


Why Patients Choose Michael Kriston DDS for Implant Restorations

Many dentists restore implants. But the cosmetic quality of the restoration — the shade matching, the abutment selection, the emergence profile, the esthetic zone classification, the attention to whether gray will show through the tissue — varies enormously from practice to practice.

Dr. Kriston brings 38 years of restorative and cosmetic experience to every implant case. He treats implant restorations with the same artistic precision as veneers and smile makeovers, because the standard should be the same: invisible, natural, beautiful.

His practice is equipped with a Carestream 3D CBCT scanner for implant planning and a Medit intraoral scanner for precise digital impressions. He performs atraumatic extractions and bone grafting to preserve the bone needed for ideal restorations. And he offers oral conscious sedation for patients who want a more comfortable experience during the restorative process.

From the extraction through the bone graft, through the implant planning, through the final crown — your case is designed and managed by one doctor with one cosmetic vision.

Before & After

No items found.
Actual patients of Michael Kriston DDS. Individual results may vary. All cases performed in our Danville, CA office.

See Our Results

Schedule Your Implant Restoration Consultation

Whether you’ve already had an implant placed and need a restoration, you’re exploring implants for the first time, or you’re unhappy with the appearance of an existing implant restoration, Dr. Kriston can help. Schedule a complimentary consultation at our Danville office.

Call (925) 838-2900 or book online. We welcome patients from Danville, San Ramon, Blackhawk, Alamo, Walnut Creek, Dublin, Pleasanton, and throughout the Tri-Valley and East Bay.

Call: (925) 838-2900